Quick answer
An IGF-1 blood test can help a clinician evaluate the growth-hormone system, but the number has meaning only beside the laboratory’s age-adjusted reference range and the person’s clinical context. Different assays and laboratories can produce meaningfully different results.
The test cannot diagnose a condition by itself, rank health on a higher-is-better scale, or prove that a product contains IGF-1 LR3. It also does not convert animal or cell experiments involving IGF-1 LR3 into human benefits. Filipino readers should treat the report as one clinical clue that may require professional interpretation and repeat testing.123
What does an IGF-1 test measure?
The test measures circulating insulin-like growth factor 1, a hormone influenced by growth-hormone signaling. Because IGF-1 is steadier than the body’s pulsing growth-hormone release, clinicians use it in specific endocrine evaluations.
An Endocrine Society guideline recommends IGF-1 measurement when clinical features suggest acromegaly or certain related conditions. It advises against using a random growth-hormone result alone to make that diagnosis.1
Acromegaly is a disorder of excessive growth-hormone activity, usually evaluated through symptoms, examination, biochemical testing, and sometimes imaging. The guideline context is diagnostic medicine, not fitness tracking or product monitoring.
The number on a report therefore answers a limited question: how the sample compared with the method’s expected range. It does not explain the cause of an unusual result on its own.
Readers researching IGF-1 LR3 can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
Why do age and the reference range matter?
IGF-1 changes across life. A multicenter study found that levels rose toward a pubertal peak and declined later in life. The researchers created age- and sex-adjusted intervals for the particular method they studied.4
This makes a raw value difficult to interpret outside the report. A number that is expected for one age group may be unusual for another. Copying a cutoff from a forum or foreign laboratory can ignore the method and population behind it.
An international assay consensus also highlights age ranges, pubertal stage, body mass index, assay performance, and comparability as relevant factors. These variables do not provide a personal diagnosis, but they explain why context belongs beside the value.5
Reference ranges are not universal targets. They describe how a validated method classifies results in a defined population. They should not be treated as a leaderboard where moving toward the upper edge always means better health.
For a Filipino reader, the practical source is the range printed by the laboratory that processed the sample, followed by clinical interpretation. An online range from another country or assay may not be directly comparable.
Can two laboratories disagree?
Yes. A review of IGF-1 testing reports substantial variation across assays, procedures, and laboratories. Robust method-specific reference ranges are necessary for interpretation.3
Differences can arise from calibration, sample handling, analytical platforms, and the reference population. This is why a change between two reports may reflect more than a change inside the body.
An international consensus on acromegaly says equivocal findings may require repeat IGF-1 measurement with the same validated assay and additional assessment. It also emphasizes reading biochemistry in clinical context.2
Repeating with the same method makes trends easier to compare. It does not guarantee a diagnosis, and it does not replace the clinician’s task of considering symptoms, medicines, other conditions, and related tests.
The safest reading of an unexpected result is not immediate self-treatment. It is confirmation that the report, reference interval, timing, and clinical question all match.
Is a blood IGF-1 result the same as IGF-1 LR3?
No. IGF-1 LR3 is a synthetic, lengthened analogue used in laboratory research. A Chinese hamster ovary cell study described the compound in that research context while examining receptor signaling.6
A standard IGF-1 blood test does not authenticate a catalog item, establish what a catalog item contains, or prove that an analogue produced the measured value. Product identity and clinical laboratory interpretation are separate problems.
The name similarity can create a false shortcut. “IGF-1” on a report refers to the analyte measured by the assay. “IGF-1 LR3” names a modified research molecule. Readers should not assume that evidence or reference ranges transfer between them.
Readers comparing this topic with CJC-1295 with DAC can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
What do the animal studies actually show?
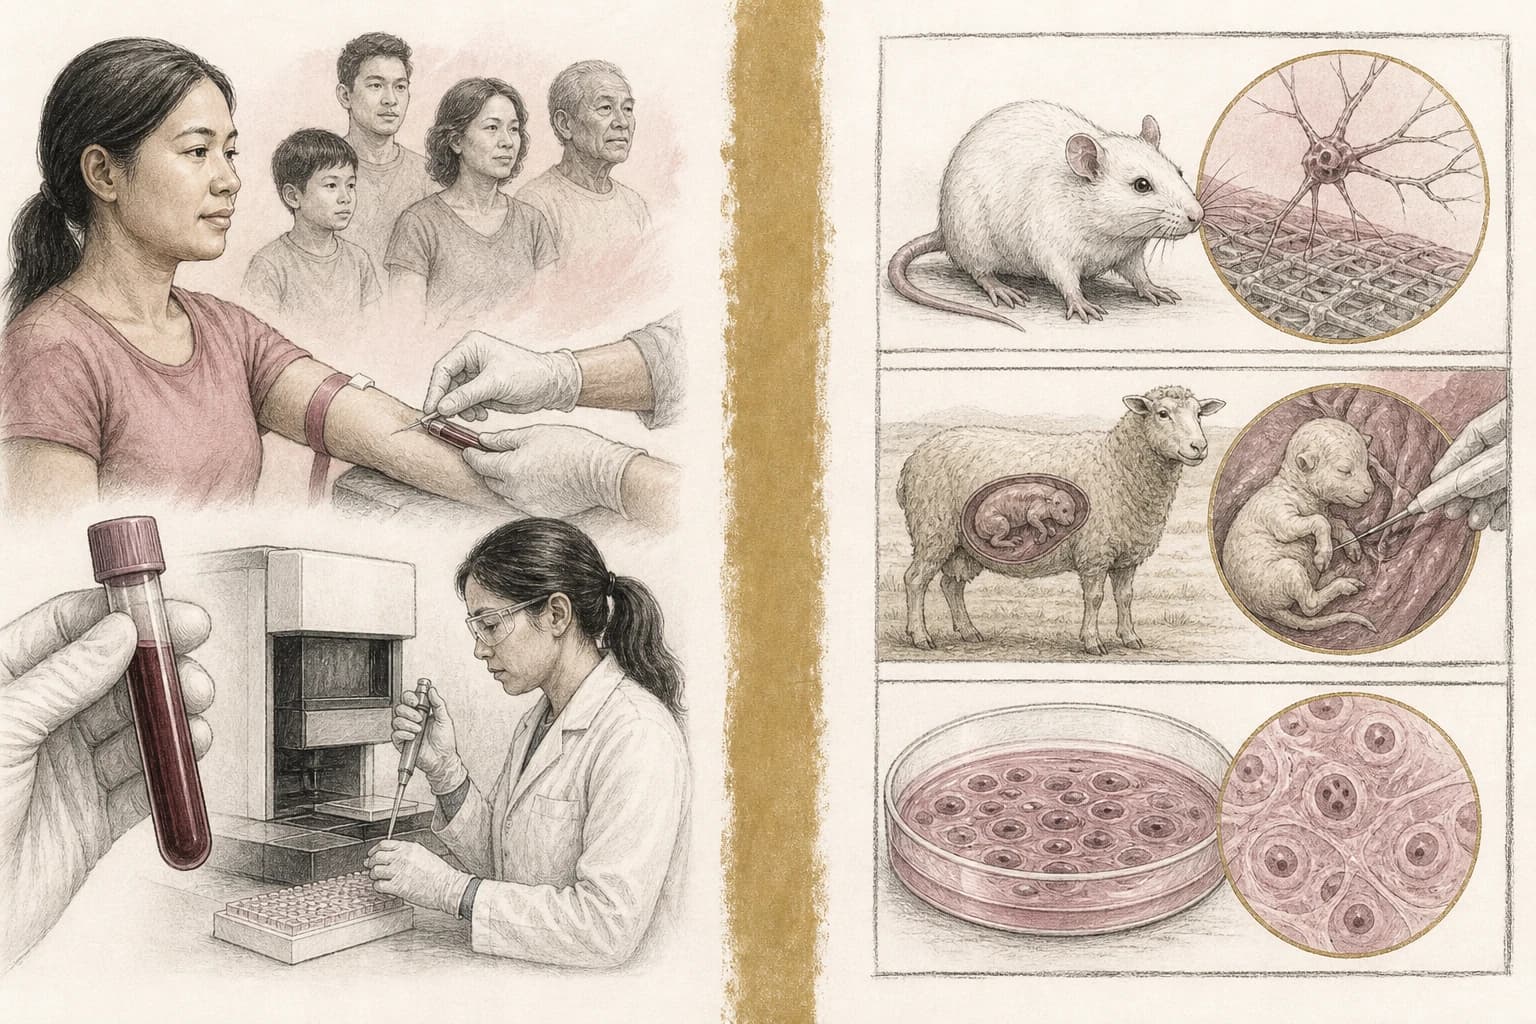
One rat study used a biomaterial conduit that released IGF-1 LR3 around an injured sciatic nerve. It reported improved experimental regeneration measures. This was an animal tissue-engineering experiment, not a human blood-test study.7
A fetal-sheep study produced a different result. IGF-1 LR3 did not improve growth compared with vehicle, and circulating amino acids were lower in the experimental group.8
Another fetal-sheep experiment found lower plasma insulin and lower glucose-stimulated insulin secretion during an acute infusion. Isolated islets collected from the animals did not differ, leaving a mixed in-vivo and laboratory pattern.9
These studies ask specialized developmental, metabolic, and biomaterials questions. They do not tell a Filipino reader what one clinical IGF-1 result means, nor do they establish human muscle, nerve, or growth benefits.
What should you check on an IGF-1 report?
Check the unit, result, age-adjusted reference interval, laboratory, and collection date. A bare number shared in a screenshot is missing much of the information needed for interpretation.
Ask why the test was ordered. Clinical guidance uses IGF-1 within defined endocrine evaluations, not as a universal wellness score.12
If the result is close to a boundary or conflicts with symptoms, a clinician may consider repeat testing with the same validated assay and other assessment. The consensus supports that cautious approach for equivocal findings.2
Do not use the result to verify an imported research product. Identity requires validated chemical and supply-chain evidence, while a blood result can be influenced by normal biology, disease, and assay variation.
Finally, keep research stages separate. Cell signaling, fetal-sheep metabolism, rat nerve repair, and human endocrine diagnosis are four different contexts. Combining them creates confidence that no single source earned.
Bottom line
An IGF-1 blood test is a useful clinical tool when interpreted with age, the laboratory’s method-specific reference range, symptoms, and other assessment. Assay differences mean results from separate laboratories may not be directly comparable, and an equivocal value can require careful repeat testing.
The report cannot diagnose a condition alone, prove that higher is healthier, or verify an IGF-1 LR3 product. Animal and cell findings involving the analogue answer different questions. Filipino readers should keep clinical testing, research compounds, and product identity in separate evidence lanes.
Frequently asked questions
Is a high IGF-1 result automatically a diagnosis?
No. Guidelines require clinical and biochemical context, and equivocal results may need repeat measurement and other assessment.12
Should two laboratories give the same result?
Not always. IGF-1 measurements can vary across assays, procedures, and laboratories.3
Is higher IGF-1 always better?
No. IGF-1 is interpreted against age-adjusted ranges and a specific clinical question, not as a wellness score.4
Can the test confirm that a catalog item contains IGF-1 LR3?
No. A clinical blood assay and chemical product-identity testing serve different purposes.
Do the two cards recommend combining IGF-1 LR3 and CJC-1295?
No. They are separate catalog references and do not recommend combinations, amount guidance, treatment, or human use.
Sources
Footnotes
-
Acromegaly: An Endocrine Society Clinical Practice Guideline. Clinical practice guideline for acromegaly. This supports the guideline's disease-specific testing context, not self-diagnosis from a report. ↩ ↩2 ↩3 ↩4
-
Consensus on criteria for acromegaly diagnosis and remission. International expert consensus on acromegaly diagnosis and remission. The guidance applies to clinical evaluation of acromegaly. ↩ ↩2 ↩3 ↩4 ↩5
-
IGF-I assay methods and biologic variability: evaluation of acromegaly treatment response. Review of assay methods and biologic variability in acromegaly monitoring. This does not provide a universal numeric cutoff for every laboratory. ↩ ↩2 ↩3
-
Reference intervals for insulin-like growth factor-1 from birth to senescence. Multicenter reference-interval study using one automated IGF-I immunoassay. Reference intervals are method-specific. ↩ ↩2
-
Consensus statement on the standardization and evaluation of growth hormone and insulin-like growth factor assays. International laboratory-assay consensus. It addresses measurement and interpretation, not a personal diagnosis. ↩
-
N-Linked Glycosylation in Chinese Hamster Ovary Cells Is Critical for Insulin-like Growth Factor 1 Signaling. Chinese hamster ovary cell experiment. Cell-signaling findings are not a clinical interpretation of a blood report. ↩
-
Revolutionary decellularized Alstroemeria stem-based nerve conduit integrated with GelMA and controlled IGF-1 LR3 release for enhanced rat sciatic nerve regeneration. Rat sciatic-nerve experimental model. Animal biomaterials findings do not establish a human outcome or a blood-test interpretation. ↩
-
IGF-1 LR3 does not promote growth in late-gestation growth-restricted fetal sheep. Late-gestation fetal-sheep growth-restriction model. The finding is animal research and includes a negative growth result. ↩
-
Attenuated glucose-stimulated insulin secretion during an acute IGF-1 LR3 infusion into fetal sheep does not persist in isolated islets. Fetal-sheep experiment with in vivo and isolated-islet measurements. The mixed experimental findings are not human clinical outcomes. ↩