TL;DR
- A 12-week routine-care study found that fat accounted for about 78% of total weight loss, while soft lean mass also decreased.1
- A systematic review of 20 randomized trials estimated that lean mass represented 25.4% of weight lost with tirzepatide.2
- A small Japanese cohort found a lower skeletal muscle index, showing why the population and measurement method remain important.3
- Body-composition results depend on the population, follow-up, measurement method, and whether changes are reported as kilograms, percentages, or body-size-adjusted indices, so comparisons need care.4
For Filipino readers, a lower number on the timbangan may seem like the clearest result. In one 12-week study, total weight, fat mass, and soft lean mass each changed by different amounts.1 Tirzepatide research therefore needs a closer reading: what changed, how researchers measured it, who participated, and how long each study followed them.4 Those details help separate a useful group average from a prediction about one person.2
First, what does body composition mean?
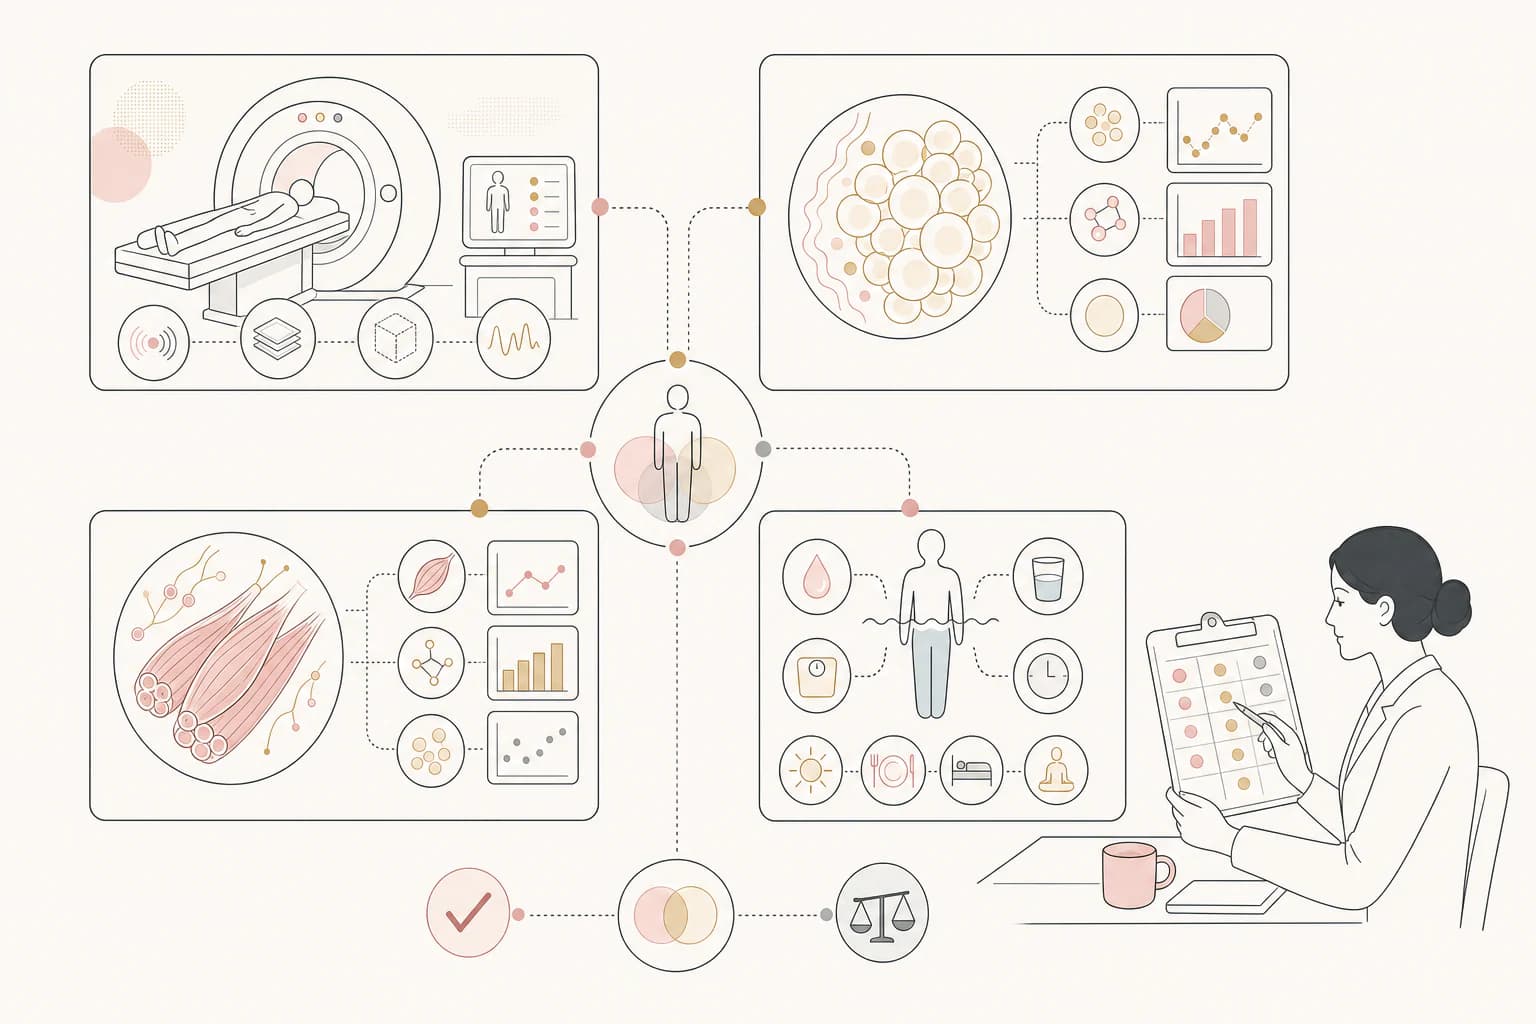
Body composition separates total weight into estimated compartments, commonly fat mass and fat-free or lean mass.4 Lean mass is not identical to skeletal muscle because it also includes water, organs, and other non-fat tissue.4 The cited studies used bioelectrical impedance, dual-energy X-ray absorptiometry, or magnetic resonance imaging.4 Those methods do not produce perfectly interchangeable numbers.4 Results may be reported in kilograms, percentages, or indices adjusted for body size.4 A person can lose lean mass in kilograms while lean mass becomes a larger share of a smaller body.1 That mathematical distinction explains why “relative preservation” can coexist with some absolute lean-tissue loss.1
For a neutral catalog reference related to this explainer, see tirzepatide.
The clearest pattern: more fat loss than lean loss
A small routine-care study followed 51 adults with obesity for 12 weeks.1 Bioelectrical impedance estimated an average 8.75-kilogram weight decrease.1 Fat mass fell by 6.87 kilograms, while soft lean mass fell by 1.73 kilograms.1 The researchers calculated that fat represented about 78% of total weight lost.1 Meanwhile, lean mass rose as a percentage of the participants’ smaller bodies.1
That result supports a careful statement: fat dominated the measured change in this cohort.1 It does not support saying lean tissue was untouched.1 The study was observational, involved only 51 people, and lasted three months.1 Bioelectrical impedance also estimates compartments through electrical properties and body-water assumptions.4 The numbers are useful evidence, but they are not a universal forecast for every reader.4
What pooled randomized evidence adds
A systematic review combined 20 randomized trials with 15,782 participants.2 Included studies measured body composition with dual-energy X-ray absorptiometry or magnetic resonance imaging.2 The authors estimated that lean mass comprised 25.4% of total weight lost with tirzepatide.2 Across incretin-based medicines, pooled lean-mass shares ranged from 25% to 39%.2
The tirzepatide estimate was broadly comparable with the pooled figure for intensive lifestyle intervention.5 However, that comparison came across separate trials, not one head-to-head experiment.5 The review also reported moderate statistical heterogeneity.2 In plain language, results differed meaningfully among the included studies.2 A pooled percentage summarizes groups; it cannot tell one person exactly how much fat or lean tissue changed.2
Other reviews point in the same broad direction
A 43-trial network meta-analysis assessed adults with overweight or obesity, with or without type 2 diabetes.6 Injectable incretin-based medicines reduced total body fat and several regional fat measures compared with control groups.6 The analysis also detected a lean-mass reduction for one studied tirzepatide regimen.6
Another network meta-analysis covered 41 randomized trials of antidiabetic medicines.7 It estimated that tirzepatide reduced fat mass and lean body mass compared with placebo.7 Network analyses combine direct trial comparisons with indirect links across a larger group of studies.6 That approach expands comparison, but it also makes results dependent on trial similarity and modeling choices.6 The 41-trial analysis therefore supports a specific finding: its tirzepatide estimate included decreases in both compartments.7 It does not make every study population or measurement method equivalent.4
Why routine-care studies can look inconsistent
A four-month observational study included 52 people with obesity.8 It reported significant fat-mass reduction, while lean-mass and handgrip changes were not statistically significant.8 That is different from proving that no lean-mass change occurred.8 A small study may lack the precision needed to separate a modest change from random variation.8
A one-year prospective routine-care study followed 164 adults.9 It reported lower fat mass and relative preservation of fat-free mass.9 However, variation in fat-free-mass change was wide, and there was no randomized comparison group.9 A Japanese retrospective cohort of 24 adults found decreases in body fat index and skeletal muscle index.3 All participants had obesity and type 2 diabetes, and most had used another incretin medicine before tirzepatide.3 Different participants, timelines, and methods can reasonably produce different estimates.4
The semaglutide comparison remains unsettled
One large observational preprint compared tirzepatide with semaglutide in routine-care records.10 Its main analysis included 7,965 people with paired body-composition measurements over 12 months.10 The authors reported greater relative lean-body-mass decline with tirzepatide at measured time points.10 They also used automated extraction from electronic health records.10
This finding deserves attention, but its status matters.10 The report was a preprint and had not completed peer review.10 Treatment choice was not randomized, so measured and unmeasured group differences could affect the result.10 Only a small fraction of the much larger record set had paired measurements.10 The comparison raises a research question; it does not settle a causal difference between the two medicines.10
For a neutral catalog reference related to that comparison, see semaglutide.
Lean mass is not the same as strength
Body-composition scans and physical function answer different questions.8 The four-month cohort measured both bioimpedance and handgrip strength.8 It found no statistically significant change in either lean mass or grip strength.8 Still, its small size limits how confidently subtle changes can be excluded.8
The distinction also appears in combination research.11 A randomized phase 2 trial studied 102 adults receiving tirzepatide with either apitegromab or placebo.11 At 24 weeks, the apitegromab combination group lost 1.9 kilograms less lean mass, while total weight loss was similar.11 This was evidence about a combination, not tirzepatide alone.11 It also did not establish lasting improvements in strength, mobility, or daily function.11 Preserving a measured compartment and preserving what a body can do are related ideas, but they are not interchangeable outcomes.11
How to read the next body-composition headline
Start with the population.4 Adults with obesity alone may differ from adults who also have type 2 diabetes.3 A 12-week routine-care cohort cannot answer the same questions as a long randomized trial.1 A preprint should carry more uncertainty than a peer-reviewed systematic review.10
Next, check the measurement and unit.4 Bioelectrical impedance, dual-energy X-ray absorptiometry, and magnetic resonance imaging estimate body compartments differently.4 Kilograms of lean mass are not the same outcome as lean mass percentage or a height-adjusted muscle index.4 Finally, look for a comparator and the range of results, not only an average.2 These checks help reconcile apparently conflicting headlines without forcing the evidence into a simple “preserved” or “lost” label.4
Bottom line
The most defensible conclusion is measured, not dramatic. In the 12-week cohort, fat accounted for about 78% of weight loss and soft lean mass also fell.1 Pooled randomized evidence placed tirzepatide’s lean-mass share near one-quarter of total weight loss.2 One routine-care study reported relative fat-free-mass preservation.9 A separate small cohort reported a lower skeletal muscle index.3 Those differences reflect populations, timelines, statistical precision, and measurement choices.4 The apitegromab trial tested a combination rather than tirzepatide alone.11 The semaglutide comparison came from an observational preprint rather than a randomized trial.10 Body composition offers more detail than scale weight, but no single percentage tells the whole story.4
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Frequently asked questions
Does tirzepatide-associated weight loss come only from fat?
No. In the 12-week routine-care study, fat accounted for about 78% of total weight loss.1 Soft lean mass also decreased in that same cohort.1 A 41-trial network meta-analysis separately estimated reductions in both fat mass and lean body mass compared with placebo.7 This study-to-study heterogeneity cannot predict one person’s result.4
Is lean mass the same as muscle?
Not exactly. Lean or fat-free mass includes more than skeletal muscle, including body water and organs.4 Some studies report total lean mass, while others use a skeletal muscle index.3 Those outcomes should not be treated as interchangeable, especially when comparing headlines from different methods.4
Why can lean mass fall while its percentage rises?
The denominator changes when total body weight decreases.1 In the 12-week cohort, participants lost some soft lean mass in kilograms.1 Yet lean mass became a larger fraction of their smaller bodies.1 Absolute change and relative share can therefore move in different directions.1
Do studies prove tirzepatide preserves strength?
The evidence here does not support that broad conclusion.8 One small routine-care cohort found no statistically significant handgrip change over four months.8 That finding came from 52 participants without a randomized comparison.8 Strength, mobility, and measured lean mass remain distinct outcomes.11
Is tirzepatide worse than semaglutide for lean mass?
An observational preprint reported greater relative lean-body-mass decline with tirzepatide in routine-care data.10 However, it was not peer reviewed, treatment was not randomized, and only selected records had paired measurements.10 It raises a useful comparative question but does not establish a definitive causal ranking.10
What evidence deserves the most cautious reading?
Small uncontrolled cohorts need caution because chance, selection, and other changes can shape results.8 Retrospective records can carry confounding and incomplete measurement.3 Preprints have not completed peer review.10 Combination trials answer questions about the combined intervention, not tirzepatide by itself.11
Sources
Read the full article: ARTICLE_URL
Footnotes
-
Early changes in body composition with tirzepatide in adults with obesity: a real-world BIA study.. Human, observational, real-world study using bioelectrical impedance analysis. The cohort was small, follow-up was short, and bioelectrical impedance provides an estimate rather than a direct tissue measurement. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15 ↩16 ↩17 ↩18 ↩19 ↩20
-
Lean Mass Changes With Incretin Therapy Versus Lifestyle Intervention: A Systematic Review and Meta-Analysis of Randomised Controlled Trials.. Human systematic review and meta-analysis of randomized trials using DXA or MRI. The pooled analysis reported moderate heterogeneity, so the estimate is not an individual prediction. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
Impact of tirzepatide on systemic arterial stiffness assessed by cardio-ankle vascular index in individuals with obesity complicated by type 2 diabetes: A retrospective cohort study in Japan.. Human retrospective observational cohort of 24 people using bioelectrical impedance. The sample was very small, most participants had prior incretin exposure, and the finding may not generalize. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Early changes in body composition with tirzepatide in adults with obesity: a real-world BIA study.; [Tirzepatide in real-world clinical practice: changes in body composition and muscle function in patients with obesity].; Effects of Tirzepatide on Body Composition, Metabolic Parameters, and Sleep Outcomes: A Real-World One-Year Prospective Study.; Impact of tirzepatide on systemic arterial stiffness assessed by cardio-ankle vascular index in individuals with obesity complicated by type 2 diabetes: A retrospective cohort study in Japan.; Comparative Effects of Individual Glucagon-Like Peptide-1 Receptor Agonist-Based Medications on Direct Measurement of Body Composition Among Adults With Overweight or Obesity With or Without Type 2 Diabetes: A Systematic Review and Network Meta-Analysis of Randomised Controlled Trials.; Lean Mass Changes With Incretin Therapy Versus Lifestyle Intervention: A Systematic Review and Meta-Analysis of Randomised Controlled Trials.. Synthesis of human observational cohorts and systematic reviews using bioimpedance, DXA, or MRI. This is an interpretive synthesis rather than a single prespecified study outcome. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15 ↩16 ↩17 ↩18 ↩19 ↩20 ↩21
-
Lean Mass Changes With Incretin Therapy Versus Lifestyle Intervention: A Systematic Review and Meta-Analysis of Randomised Controlled Trials.. Indirect comparison within a systematic review of randomized trials. The intervention groups came from different trials, and pooled averages do not establish equivalence for every person. ↩ ↩2
-
Comparative Effects of Individual Glucagon-Like Peptide-1 Receptor Agonist-Based Medications on Direct Measurement of Body Composition Among Adults With Overweight or Obesity With or Without Type 2 Diabetes: A Systematic Review and Network Meta-Analysis of Randomised Controlled Trials.. Human systematic review and network meta-analysis of randomized controlled trials. Network estimates combine direct and indirect comparisons and should not be generalized across every regimen. ↩ ↩2 ↩3 ↩4 ↩5
-
Comparative Effects of Antidiabetic Drugs on Body Composition: A Systematic Review and Network Meta-Analysis.. Human systematic review and network meta-analysis of randomized controlled trials. The review combined trials of antidiabetic medicines, and results depend on included populations and measurement methods. ↩ ↩2 ↩3 ↩4
-
[Tirzepatide in real-world clinical practice: changes in body composition and muscle function in patients with obesity].. Human observational study using bioimpedance and handgrip dynamometry. A non-significant change does not prove no change, especially in a small uncontrolled cohort. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12
-
Effects of Tirzepatide on Body Composition, Metabolic Parameters, and Sleep Outcomes: A Real-World One-Year Prospective Study.. Human prospective observational study using bioelectrical impedance-derived measures. The large variability in fat-free-mass change and lack of randomization limit causal interpretation. ↩ ↩2 ↩3 ↩4
-
Greater lean-body-mass decline with tirzepatide than semaglutide in routine care, revealed by body-composition digital phenotyping. Human observational preprint using electronic health records and digitally extracted body-composition measurements. It was not peer reviewed, treatment was not randomized, and digital extraction may introduce measurement or selection bias. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15
-
Apitegromab for lean mass preservation during tirzepatide-induced weight loss: a randomized, double-blind, placebo-controlled phase 2 trial.. Human randomized, double-blind, placebo-controlled phase 2 combination trial in 102 adults. This tests an investigational combination, not tirzepatide alone, and does not establish long-term functional benefit. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9