Quick answer
Total testosterone and fertility markers answer different questions. In short comparative trials, both enclomiphene and testosterone gel raised testosterone in selected men with secondary hypogonadism. Their signaling patterns diverged: enclomiphene increased LH and FSH and maintained or increased sperm concentration, while testosterone gel suppressed gonadotropins and reduced spermatogenesis. Sperm concentration still does not prove conception, pregnancy, or live birth. A “normal” testosterone number cannot by itself describe reproductive potential, symptoms, safety, or long-term outcomes.123
Why isn’t testosterone the whole fertility story?
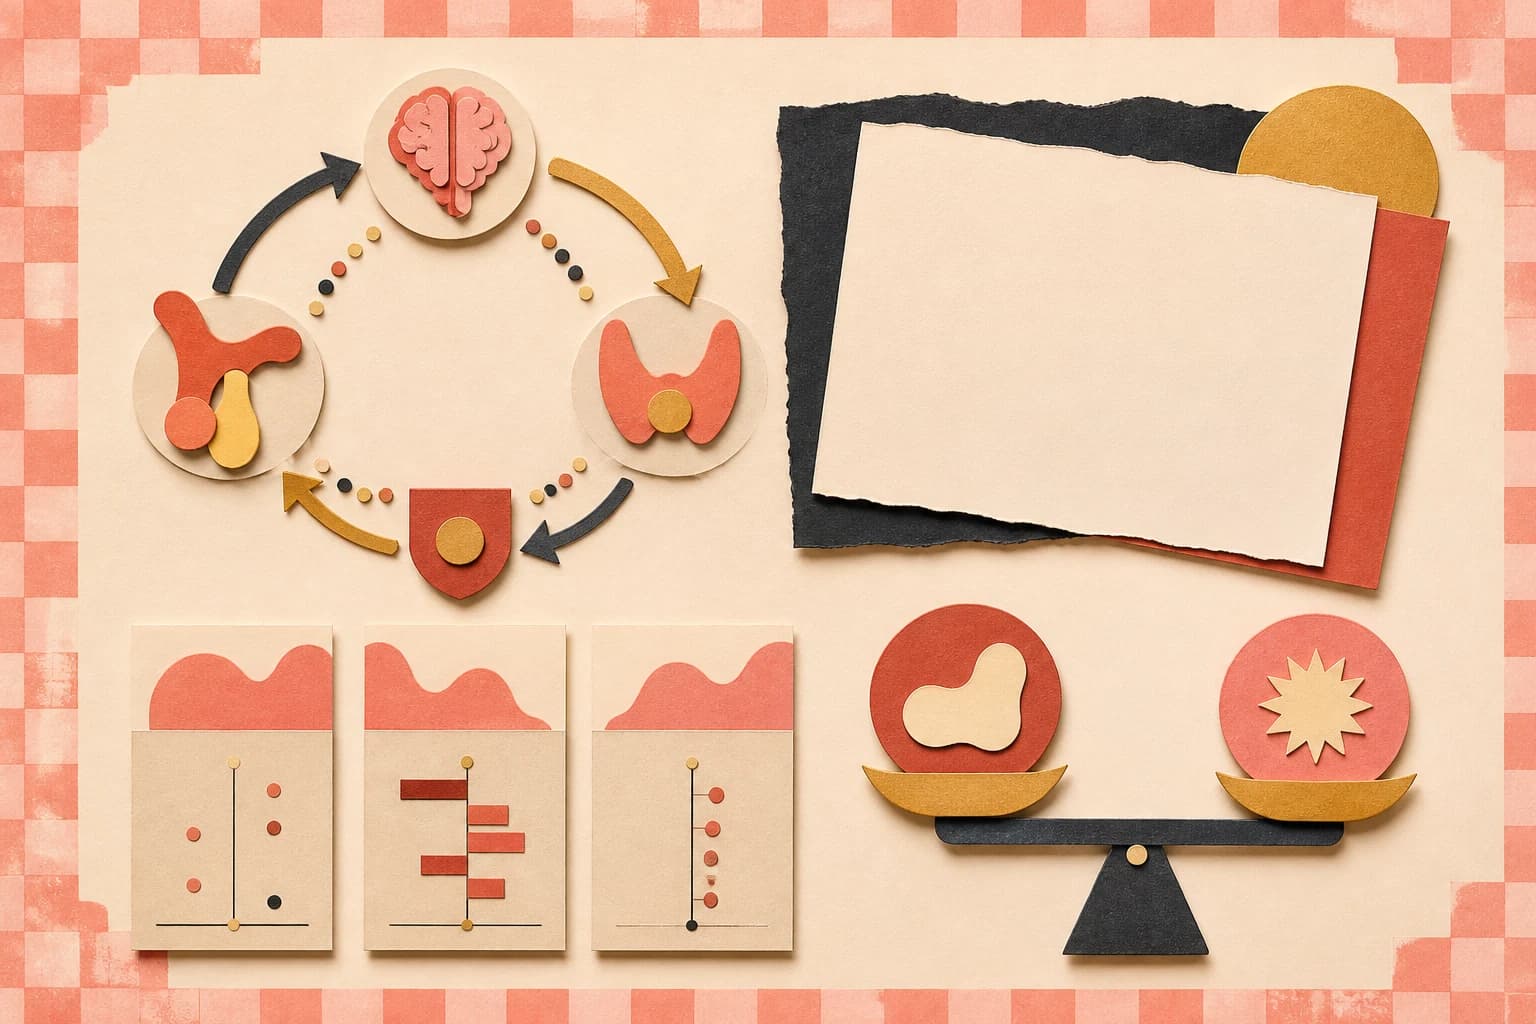
Testosterone is essential to male reproductive biology, but a blood level is only one part of a feedback system.
The brain and pituitary release signals that tell the testes what to do. LH supports testosterone production, while FSH participates in sperm development.
External testosterone can raise the measured blood level while reducing LH and FSH. That pattern can weaken the internal signals needed for sperm production.2
This is why two approaches can produce similar total-testosterone numbers but different semen outcomes.
Fertility also depends on sperm movement, shape, total number, anatomy, timing, partner factors, and many other conditions.
The headline lesson is simple: a laboratory number can look reassuring while a different part of the system moves in the opposite direction.
Readers researching Enclomiphene can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
What did the comparative trials find?
In phase II and phase III trials, both enclomiphene and testosterone gel raised total testosterone in selected men with secondary hypogonadism.1
That common endpoint does not make the interventions equivalent. Similar hormone changes cannot establish equal symptoms, safety, fertility, or long-term results.1
Enclomiphene increased LH and FSH, while testosterone gel suppressed gonadotropin signaling.2
The different pattern is consistent with stimulation of internal hormone production versus external hormone replacement. It still needs to be tied to actual outcomes.
The trials were short and enrolled defined populations. They do not describe people with every cause of low testosterone or anyone using an unidentified product.
Timing can change the apparent comparison. Testosterone varies across the day, while semen production unfolds over a much longer biological cycle. A study needs schedules appropriate to each marker. Measuring both on one convenient date does not give them equal meaning.
Laboratory methods matter as well. Different assays and semen-analysis procedures can introduce variation. A trustworthy paper reports how samples were collected and analyzed rather than presenting every number as perfectly interchangeable.
When an article reports only total testosterone, it removes the very markers that made these comparisons scientifically interesting.
What happened to sperm concentration?
Enclomiphene maintained or increased sperm concentration in the cited trials. Testosterone gel reduced spermatogenesis or did not maintain the same sperm-count pattern.3
Sperm concentration measures how many sperm are present in a volume of semen. It does not describe every feature required for fertility.
The endpoint also does not prove conception, pregnancy, or live birth.3 Those outcomes depend on both partners and a longer chain of events.
Still, the difference is clinically relevant when fertility is a goal. It shows why hormone replacement decisions cannot be based only on the desired blood number.
Guidelines recommend against starting testosterone therapy in men planning fertility in the near term.4 That is a general guideline statement, not personal advice.
What did the meta-analysis clarify?
A randomized-trial meta-analysis found no significant total-testosterone difference between pooled clomiphene or enclomiphene groups and testosterone gel.5
At the same time, gonadotropin effects differed.5 This is a useful example of why one headline endpoint can hide a meaningful biological contrast.
The pooled SERM category included clomiphene and enclomiphene. It should not be presented as pure enclomiphene evidence for every outcome.
Meta-analysis can improve precision, but it inherits the populations, durations, and measurement choices of its included trials.
It also focused mainly on biochemical measures. The result cannot automatically answer symptom relief, partner pregnancy, or long-term safety.
The fairest interpretation keeps both findings together: similar pooled total testosterone, different upstream hormone signaling.
Which fertility endpoints are strongest?
LH and FSH show signaling. They are useful, but they are not direct proof of fertility.
Sperm concentration moves closer to reproductive function, yet it still omits movement, shape, and other semen features.
Total motile sperm count combines more information. Fertilization, pregnancy, and live birth are progressively more patient-important outcomes.
Each step answers a different question and usually requires larger, longer, and more complex research.
Semen measurements also vary within the same person. Collection conditions, recent fever, abstinence interval, laboratory handling, and ordinary biological variation can influence a result. Repeated testing may provide a more stable picture than a single sample.
Pregnancy research becomes more complex because outcomes belong to a couple, not one isolated laboratory value. Studies need enough time and careful reporting of partner factors. A medicine-centered headline can hide that shared context.
An article should name the actual rung on that ladder. It should not jump from a hormone rise to “preserves fertility” without qualification.
What should Filipino readers verify?
The Philippine FDA Verification Portal lists establishment licenses separately from registered or notified health products.6
Confirm the exact product name, manufacturer, form, registration details, and record dates. A matching seller name does not authenticate a specific item.
WHO states that some falsified medical products can closely resemble genuine ones and may require laboratory analysis.7
This matters because fertility claims often create urgency. Packaging and testimonials can feel persuasive while leaving identity unresolved.
The clinical trial, exact molecule, and local record should remain linked to their own evidence.8 None can stand in for the others.
How should someone read a hormone comparison?
Start with the diagnosis and population. These trials involved selected men with secondary hypogonadism, not general optimization.
List every measured hormone, not only total testosterone. LH and FSH explain the pathway difference.2
Find the fertility endpoint. Sperm concentration is meaningful but remains short of pregnancy or live birth.3
Check duration, dropouts, adverse events, and formulation. A short favorable pattern cannot settle long-term use.
Finally, identify whether the conclusion comes from enclomiphene alone or a pooled clomiphene/enclomiphene category.5
Readers comparing this topic with hCG can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
Bottom line
Enclomiphene and testosterone gel both raised total testosterone in short studies, but they did not create the same hormonal environment. Enclomiphene increased LH and FSH and maintained or increased sperm concentration, while testosterone gel suppressed gonadotropin signaling and spermatogenesis.
Those differences matter, yet sperm concentration is not pregnancy or live birth, and biomarkers are not every patient outcome. Filipino readers should also verify the exact product and local record. A responsible fertility discussion follows the whole chain—from diagnosis and hormone signaling to semen measures and patient-important outcomes—instead of celebrating one testosterone number.
Frequently asked questions
Can two treatments raise testosterone differently?
Yes. Their effects on LH, FSH, and sperm production can differ.12
Did enclomiphene preserve sperm concentration in trials?
It maintained or increased the measured concentration in the cited short studies.3
Does sperm concentration prove fertility?
No. It does not prove conception, pregnancy, or live birth.3
What did the pooled comparison find?
Total-testosterone changes were similar, while gonadotropin effects differed.5
Why is near-term fertility mentioned in testosterone guidelines?
Guidelines advise against starting testosterone therapy when near-term fertility is planned.4
Sources
Footnotes
-
Testosterone Restoration by Enclomiphene Citrate in Men with Secondary Hypogonadism: Pharmacodynamics and Pharmacokinetics; Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with low testosterone: comparison with testosterone gel; Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial comparing topical testosterone; Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone. Phase II and phase III active-comparator trials. Similar testosterone changes do not establish equivalence for symptoms, safety, long-term outcomes, or all formulations. ↩ ↩2 ↩3 ↩4
-
Testosterone Restoration by Enclomiphene Citrate in Men with Secondary Hypogonadism: Pharmacodynamics and Pharmacokinetics; Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial comparing topical testosterone; Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone. Short studies in men with secondary hypogonadism. Hormone-pattern differences do not by themselves prove a patient-important benefit. ↩ ↩2 ↩3 ↩4 ↩5
-
Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with low testosterone: comparison with testosterone gel; Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial comparing topical testosterone; Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone. Semen outcomes in small and short active-comparator trials. Sperm concentration does not prove conception, pregnancy, or live birth. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Testosterone Therapy in Men With Hypogonadism: An Endocrine Society Clinical Practice Guideline. Endocrine Society clinical practice guideline. This is a guideline statement, not a personal treatment recommendation. ↩ ↩2
-
Clomiphene or enclomiphene citrate for the treatment of male hypogonadism: a systematic review and meta-analysis of randomized controlled trials. Randomized-trial meta-analysis of SERM therapy. The pooled category includes clomiphene and enclomiphene and focuses mainly on biochemical endpoints. ↩ ↩2 ↩3 ↩4
-
Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Official Philippine regulatory verification service. A portal record applies to the exact product or establishment named in that record. ↩
-
WHO laboratory analysis of suspected falsified medical products; WHO laboratory testing for health-product regulation. WHO guidance on suspected falsified medical products and regulatory laboratory testing. Appearance alone cannot authenticate a product or establish a research outcome. ↩
-
Testosterone Restoration by Enclomiphene Citrate in Men with Secondary Hypogonadism: Pharmacodynamics and Pharmacokinetics; Oral enclomiphene citrate stimulates the endogenous production of testosterone and sperm counts in men with low testosterone: comparison with testosterone gel; Enclomiphene citrate stimulates testosterone production while preventing oligospermia: a randomized phase II clinical trial comparing topical testosterone; Oral enclomiphene citrate raises testosterone and preserves sperm counts in obese hypogonadal men, unlike topical testosterone; Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Editorial synthesis of the canonical research records and Philippine verification sources. This synthesis is educational and is not personal medical advice or a product recommendation. ↩