Quick answer
Tesamorelin’s cognitive evidence is exploratory, not established. In a six-month phase 2 trial of 73 virally suppressed adults with HIV, abdominal obesity, and neurocognitive impairment, the tesamorelin group showed a favorable cognitive trend. The between-group difference was not statistically significant.1
The same study found a clearer reduction in waist circumference, while other randomized work reported visceral- and liver-fat changes in narrow HIV subgroups.234 Those body-composition findings cannot be used as proof of a cognitive benefit. Filipino readers should keep the population, comparator, endpoint, and exact product identity attached to every claim.
Why are researchers asking a cognitive question?
Tesamorelin is a growth hormone-releasing hormone analogue studied mainly in people living with HIV and excess abdominal fat.5
Researchers have investigated whether metabolic and body-composition changes in this population relate to cognition. That is a hypothesis, not proof that changing one measure will change the other.
Neurocognitive performance covers several abilities, such as attention, memory, processing speed, and executive function. A trial must define which tests contribute to its outcome.
People living with HIV may also differ in treatment history, metabolic health, age, and other factors connected to cognitive performance.
The clinical context matters because a study in this defined population cannot be generalized to healthy adults seeking concentration or memory enhancement.
The trial question also differs from a diagnosis claim. Measuring change on a neurocognitive test does not establish the cause of a participant’s impairment or show that the same pattern applies to another condition.
This narrow framing makes the research more useful: it tells readers exactly which uncertainty investigators tried to reduce.
Readers researching Tesamorelin can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
How was the phase 2 study designed?
The six-month trial randomized 73 virally suppressed adults with HIV, abdominal obesity, and neurocognitive impairment to tesamorelin or standard care.1
It was open-label, so participants and investigators knew which group received treatment. It also lacked a placebo arm.
Randomization strengthens the comparison, but awareness of assignment can influence behavior, expectations, and some assessments. The small sample also limited statistical power.
Power refers to the chance that a study can detect a real difference of the expected size. An underpowered study may produce an uncertain estimate even when the group averages differ.
This design is appropriate for exploring a signal. It is not the final design readers would want for a broad cognitive claim.
What did the cognitive result actually say?
The tesamorelin group showed a trend toward better neurocognitive performance, but the between-group difference was not significant.1
“Trend” describes the direction of the estimate. It does not mean the trial proved an effect or nearly certain one.
A non-significant result may reflect no meaningful difference, limited precision, insufficient sample size, or a combination of factors. The study cannot choose among those explanations by wording alone.
Confidence intervals are more informative than the direction alone because they show the range of effects compatible with the sample. A larger study can narrow that range if the design and measurements remain rigorous.
Multiple cognitive tests can also raise interpretation problems. A prespecified composite protects against choosing whichever individual result looks most favorable after analysis.
The responsible conclusion is that the trial generated a hypothesis requiring a larger, more rigorous test.
It would be inaccurate to shorten this to “tesamorelin improves cognition.” That removes the comparator, uncertainty, and narrow population.
What did the waist result show?
The same trial found a greater reduction in waist circumference with tesamorelin than with standard care.2
That is a body-size outcome, not a cognitive outcome. Its clearer result does not rescue or substitute for the non-significant cognitive comparison.
Waist circumference is an accessible measure, but it does not directly measure brain function or every fat compartment.
The two outcomes can appear in one article because the trial measured both. They must remain in separate sentences with separate interpretations.
This distinction prevents a common evidence shortcut: using a positive secondary result to make the headline outcome sound positive.
What do visceral- and liver-fat studies add?
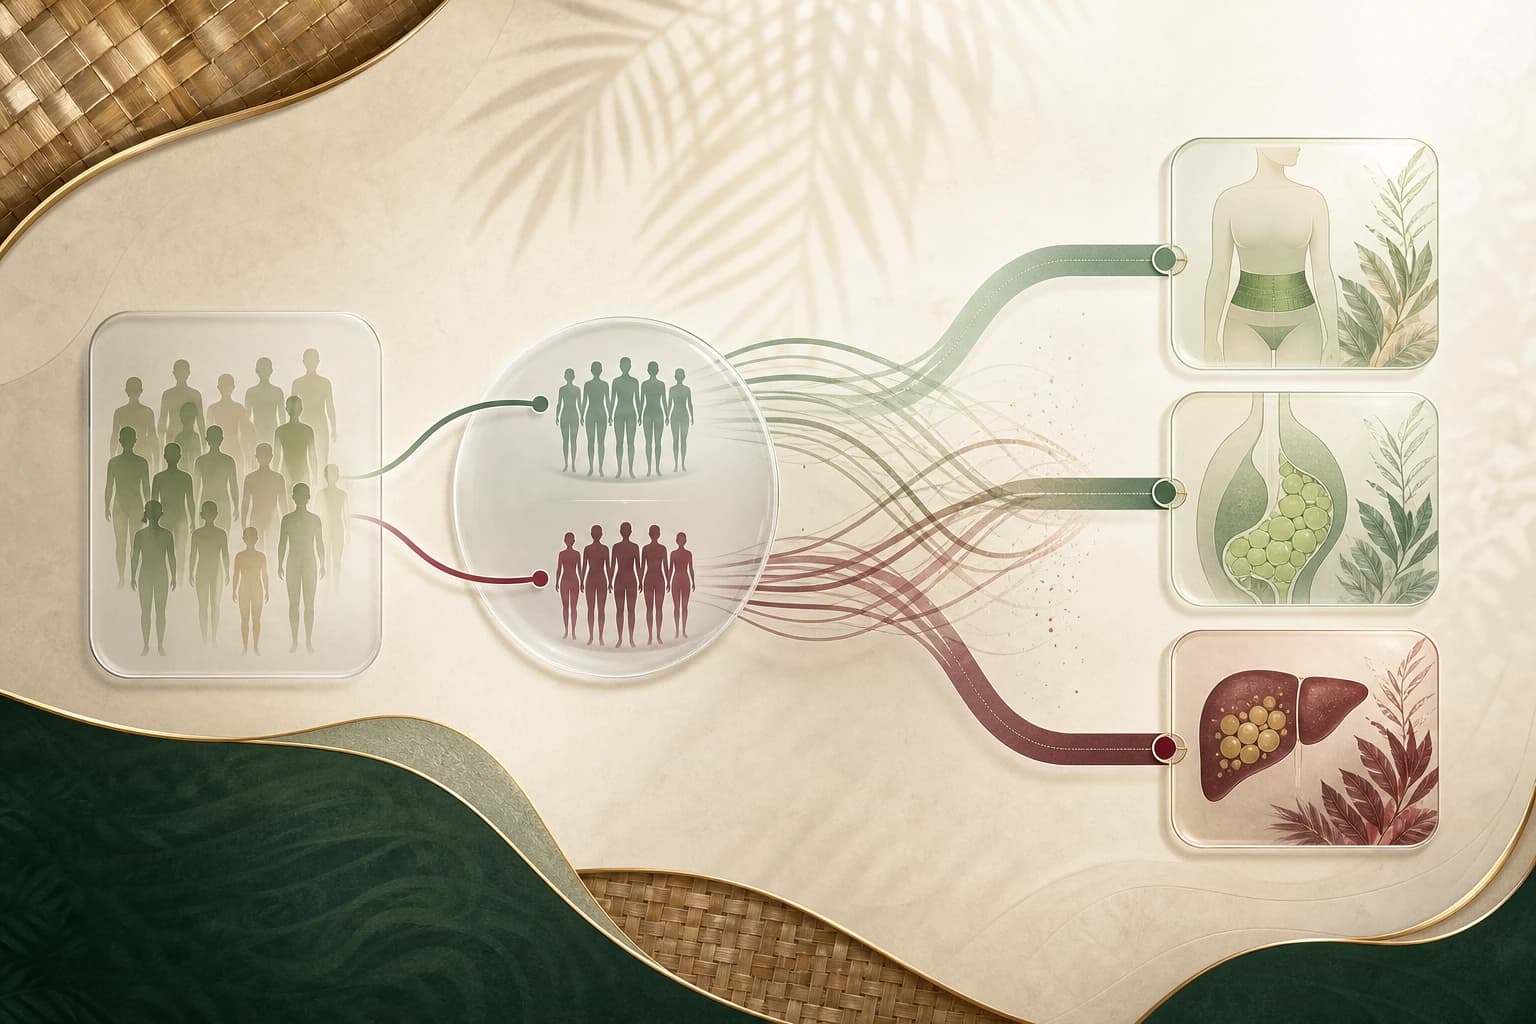
Other tesamorelin research provides stronger evidence for defined body-composition outcomes in people living with HIV.
In a randomized-trial subgroup of participants using integrase-inhibitor regimens, tesamorelin reduced visceral fat compared with placebo.3
The same small subgroup analysis also reported lower hepatic, or liver, fat.4
These findings belong to a defined HIV population and a subgroup of a parent trial. They should not be generalized to all adults or converted into cognitive claims.
They do help explain why metabolic and body-composition pathways remain scientifically interesting. They do not establish that those changes mediated any neurocognitive outcome.
What would stronger cognitive evidence require?
A confirmatory study would predefine the cognitive outcome and enroll enough participants to estimate the group difference precisely.
Blinding and a placebo comparator could reduce expectation and assessment biases. Repeated testing would need methods that consider practice effects from taking similar cognitive tests more than once.
Researchers would also need to separate cognitive change from mood, sleep, medical events, and changes in HIV treatment or metabolic health.
A mediation analysis could test whether a body-composition change statistically explains part of a cognitive result. Even then, statistical mediation is not automatically proof of a biological mechanism.
Until such evidence exists, “being investigated” is more accurate than “shown to improve.”
Replication in another site would help show whether the pattern depends on one research team or clinic. Longer follow-up could test durability, while safety and cognitive outcomes would still require separate reporting.
What should Filipino readers verify?
Ask whether an article reports the significant between-group result or only the direction of a trend.
Check that the population is named: virally suppressed adults with HIV, abdominal obesity, and neurocognitive impairment. Removing that context broadens the claim beyond the trial.
The Philippine FDA Verification Portal separates licensed establishments from registered or notified health products. Search the exact product and company record.6
WHO notes that falsified products can resemble genuine ones and may require quality-control analysis. A cognitive-study citation cannot authenticate a catalog item.7
Keep every conclusion attached to its source, endpoint, comparator, population, and exact product identity.8
Readers comparing this topic with Sermorelin can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
Bottom line
Tesamorelin’s cognitive research has produced an interesting but unconfirmed signal. A small open-label phase 2 trial found a favorable trend, yet the cognitive difference from standard care was not statistically significant. Waist circumference improved more clearly, and separate HIV studies reported visceral- and liver-fat changes.
Those body-composition findings do not prove a cognitive effect. Filipino readers should look for the actual between-group result, preserve the narrow HIV context, and verify any product separately. For now, cognition remains a research question rather than an established outcome.
Frequently asked questions
Did the phase 2 trial prove cognitive improvement?
No. The group difference was not statistically significant.1
Was the study placebo-controlled?
No. It was an open-label comparison with standard care.
Did waist circumference change?
Yes. It fell more in the tesamorelin group.2
Do visceral-fat findings prove a brain effect?
No. They are different outcomes and require separate evidence.
Do the product cards make cognitive claims?
No. They are neutral catalog references.
Sources
Footnotes
-
Effects of Tesamorelin on Neurocognitive Impairment in Persons With HIV and Abdominal Obesity.. Six-month randomized open-label trial in 73 adults with HIV and abdominal obesity. The trial was limited by insufficient power and no placebo arm. ↩ ↩2 ↩3 ↩4
-
Effects of Tesamorelin on Neurocognitive Impairment in Persons With HIV and Abdominal Obesity.. Secondary body-composition outcome in the 6-month phase 2 trial. This finding did not translate into a statistically clear cognitive advantage. ↩ ↩2 ↩3
-
Efficacy and safety of tesamorelin in people with HIV on integrase inhibitors.. Subanalysis of a randomized double-blind trial among participants on INSTI-based antiretroviral regimens. The analysis was a subgroup study within a parent trial. ↩ ↩2
-
Efficacy and safety of tesamorelin in people with HIV on integrase inhibitors.. Same randomized subanalysis in adults with HIV. This result comes from a smaller subgroup than the parent trial. ↩ ↩2
-
Effects of Tesamorelin on Neurocognitive Impairment in Persons With HIV and Abdominal Obesity.; Efficacy and safety of tesamorelin in people with HIV on integrase inhibitors.; Effects of tesamorelin on hepatic transcriptomic signatures in HIV-associated NAFLD.; Growth Hormone Releasing Hormone Reduces Circulating Markers of Immune Activation in Parallel with Effects on Hepatic Immune Pathways in Individuals with HIV-infection and Nonalcoholic Fatty Liver Disease.; The Growth Hormone Releasing Hormone Analogue, Tesamorelin, Decreases Muscle Fat and Increases Muscle Area in Adults with HIV.; Body composition, hepatic fat, metabolic, and safety outcomes of Tesamorelin, a GHRH analogue, in HIV-associated lipodystrophy: A meta-analysis of randomized controlled trials.. Human trials and meta-analysis in adults with HIV-related abdominal adiposity or lipodystrophy. This is a research role summary, not a claim about broad clinical use. ↩
-
Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Official Philippine regulatory verification service. A portal record applies to the exact product or establishment named in that record. ↩
-
WHO laboratory analysis of suspected falsified medical products; WHO laboratory testing for health-product regulation. WHO guidance on suspected falsified medical products and regulatory laboratory testing. Appearance alone cannot authenticate a product or establish a research outcome. ↩
-
Effects of Tesamorelin on Neurocognitive Impairment in Persons With HIV and Abdominal Obesity.; Efficacy and safety of tesamorelin in people with HIV on integrase inhibitors.; Effects of tesamorelin on hepatic transcriptomic signatures in HIV-associated NAFLD.; Growth Hormone Releasing Hormone Reduces Circulating Markers of Immune Activation in Parallel with Effects on Hepatic Immune Pathways in Individuals with HIV-infection and Nonalcoholic Fatty Liver Disease.; The Growth Hormone Releasing Hormone Analogue, Tesamorelin, Decreases Muscle Fat and Increases Muscle Area in Adults with HIV.; Body composition, hepatic fat, metabolic, and safety outcomes of Tesamorelin, a GHRH analogue, in HIV-associated lipodystrophy: A meta-analysis of randomized controlled trials.; Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Editorial synthesis of the canonical research records and Philippine verification sources. This synthesis is educational and is not personal medical advice or a product recommendation. ↩