
TL;DR
- Across the STEP 1–5 trial review, stomach and bowel symptoms were the most common side effects, and the review described them as generally manageable and non-severe.1
- A 511-person US clinic study recorded gastrointestinal symptoms in 50.7% of semaglutide users and 28.5% of tirzepatide users within that retrospective cohort.2
- A 208-person retrospective preprint found no significant difference in gastrointestinal-symptom severity between oral and under-the-skin semaglutide groups.3
- A report about one patient can flag an unusual event for further study, but it cannot establish how often that event occurs or whether semaglutide caused it.4
Scroll through a Filipino social feed and semaglutide can look either effortless or alarming. Everything depends on whose story appears next. A better reading starts with less dramatic questions. How many people were observed? Who were they, and for how long? The task is not deciding whether an anecdote feels believable. It is deciding how much confidence the story deserves.
Start with the denominator, not the viral story
A side-effect percentage becomes useful only when its denominator stays visible. The STEP 1–5 review covered adults with overweight or obesity. Its trials included groups with and without type 2 diabetes.1 The review identified gastrointestinal symptoms as the most common side effects. It described them as generally manageable and nonsevere.1
Those words summarize several trial settings, not one universal event rate.1 They also cannot predict one person’s experience.1 That is why the denominator belongs beside the headline. Population and study design matter too. Together, those details show what a percentage can—and cannot—say. This simple habit makes dramatic numbers easier to compare.
For readers looking for the exact topic, the Semaglutide card below shows its live catalog details. It is a catalog reference, not research evidence or a recommendation.
What the trial overview says about common symptoms
The STEP review places stomach and bowel complaints at the center of its safety summary.1 It reports that these events were generally manageable and nonsevere across the program.1 “Common” still does not mean universal. The review-level wording also cannot predict severity for one participant.1
Study summaries can blur differences when readers skip the population details. STEP trials included distinct groups with and without type 2 diabetes.1 Some also included intensive behavioral support.1 Their findings describe averages within those designs, not a rate that applies everywhere.1
This is where social-media shorthand becomes unreliable. A personal account can describe intensity vividly. Where are its trial denominator and evidence of typicality? Trial summaries answer a different question: what pattern appeared across their defined groups?
Real-world studies add messier, useful context
A retrospective study across several US health centers followed 511 adults receiving semaglutide or tirzepatide for obesity care.2 Gastrointestinal symptoms were reported by 50.7% of semaglutide users and 28.5% of tirzepatide users in that record.2 That is a comparison inside one health-system dataset, not a universal ranking of the two medicines.2
Its sample was 91.8% White and 74.8% female.5 The authors called for studies in more diverse populations.5 A separate Türkiye cohort included 500 adults with type 2 diabetes. It found similar gastrointestinal-event rates across three semaglutide exposure groups over 30 weeks.6 The cohort recorded 117 discontinuations, or 23.4%, during follow-up.7 Its abstract does not attribute every decision to side effects.7
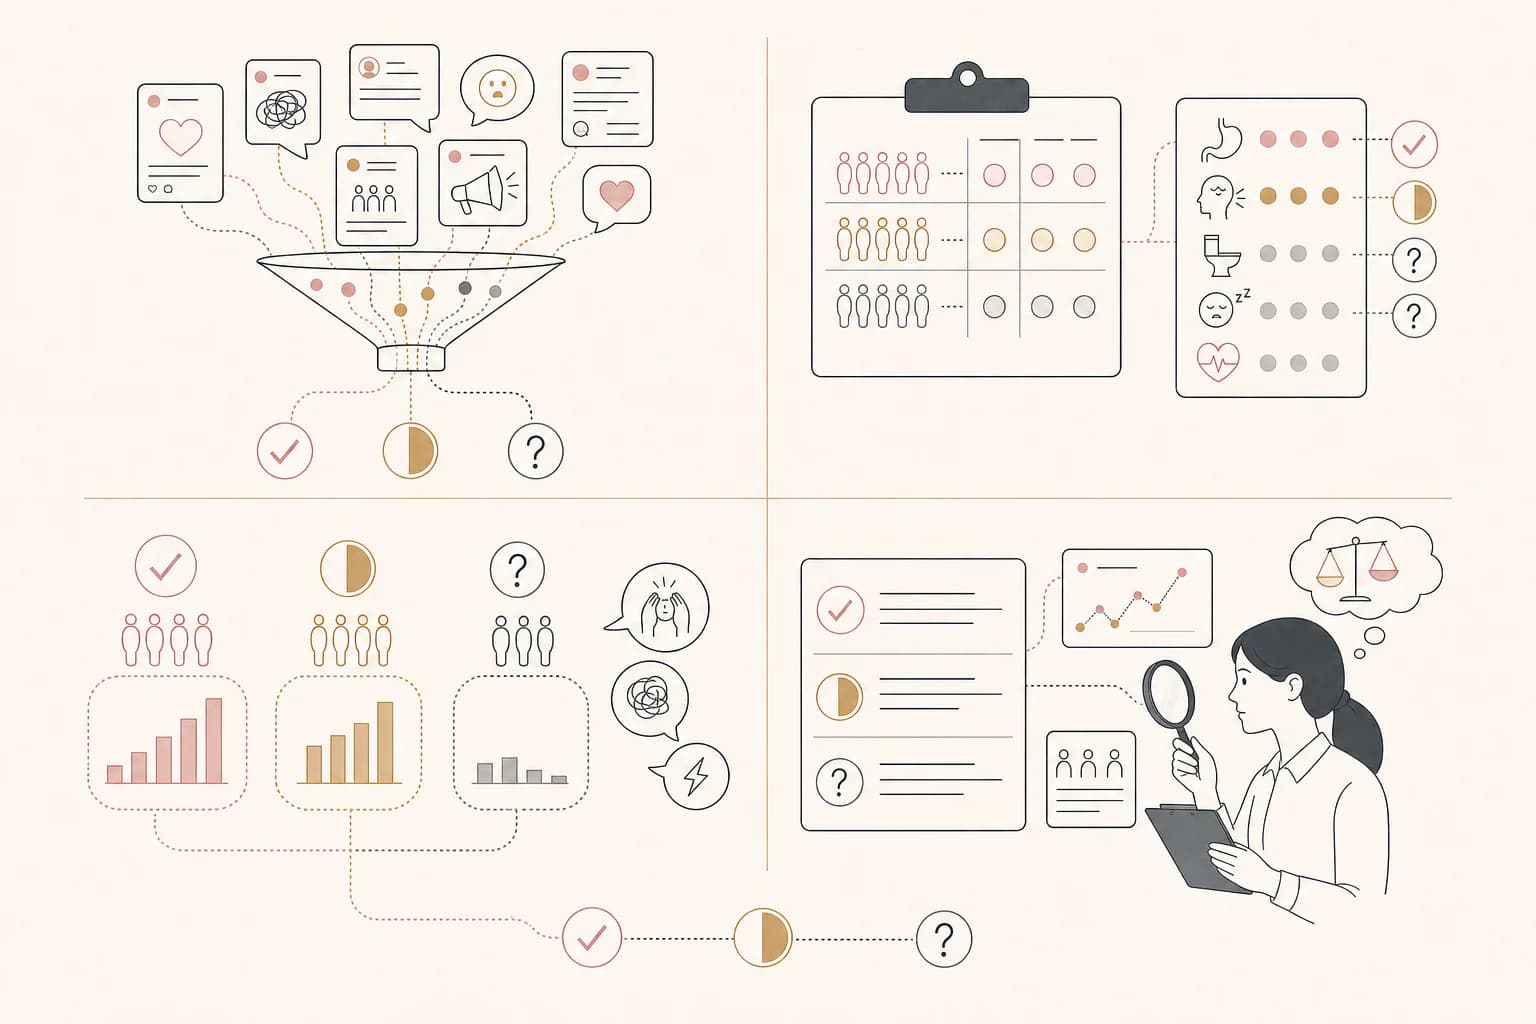
One number can look very different after its setting and population return.
Route comparisons answer a narrower question
A multicenter retrospective preprint compared 89 adults receiving oral semaglutide with 119 receiving the under-the-skin form.3 The groups had type 2 diabetes and obesity. Gastrointestinal-symptom severity did not differ significantly between them.3 Dizziness appeared more often in the under-the-skin group.8
That result does not prove the two forms have identical safety profiles in every population.3 It says only that this dataset did not find a difference in the severity of its mainly gastrointestinal adverse effects.3 Because the work is a preprint, its methods and conclusions should also be read as less settled than a fully reviewed publication.3
The route may dominate online discussion. The study design and measured outcome still set the boundary.
For readers comparing nearby catalog topics, the Tirzepatide card below opens its live catalog details. It is a separate reference, not proof of compatibility or a recommendation.
Small special-population studies are not general forecasts
A preprint based on records from 12 adults with Prader–Willi syndrome reported mild gastrointestinal symptoms in 25% of participants, with none leaving the study for that reason.9 The group was unusually small and clinically specific, so the finding cannot supply a general semaglutide side-effect rate.9
A retrospective review of 47 psychiatric inpatients receiving antipsychotic medicines likewise described gastrointestinal symptoms as the most common side effects and reported no semaglutide discontinuations because of them.10 That cohort had severe mental illness, high rates of dysglycemia, and shrinking participant counts at later follow-up points.10
These small records broaden the view beyond large general cohorts.910 Their value lies in describing what happened in those groups. Neither can turn a clinically specific sample into a promise for everyone else.910
Rare reports are signals, not frequency estimates
One case report described a 60-year-old woman whose scan showed abnormal gastric retention and gallbladder, bowel, and kidney patterns after first exposure to semaglutide.4 Clinical assessment supported suspected gastroparesis, gallbladder inflammation, bowel inflammation, and possible acute kidney injury related to dehydration, and the symptoms later resolved with supportive care and semaglutide withdrawal.4
The report documents one detailed clinical sequence.4 It cannot reveal an event rate or settle causation for a wider population.4 A case report can raise a signal while keeping the single observation visible.4 That is more disciplined than turning one experience into a typical outcome.
That distinction keeps vigilance from becoming exaggeration.
Side effects can extend beyond the obvious list
A dental review links delayed stomach emptying, reflux, nausea, vomiting, and nutritional changes with possible dry mouth, altered taste, bad breath, and enamel erosion.11 These oral findings are described as potential secondary effects, not as outcomes that every semaglutide user will experience.11
Another uncontrolled study followed 87 people who received a non-comparable semaglutide biotherapeutic and recorded any side effect in 59.4% and a major adverse effect in 9.9%.12 Because the product was explicitly non-comparable and the study lacked a control group, those figures should not be transferred to named regulated products.12
The wider lesson is simple. Keep the exact product and event definition beside each percentage.
A Philippine reader’s evidence checklist
Start by naming the design: trial review, retrospective cohort, preprint, or single case. Then find the denominator, participant profile, follow-up period, and event definition. Ask how researchers recorded symptoms. Clinic notes and a structured trial form can answer different questions.
Philippine relevance requires restraint. The largest US cohort here was 91.8% White and 74.8% female.5 Other records came from Türkiye, a UK specialist clinic, and a Canadian psychiatric center.9610 Those settings deserve to remain visible. Filipino readers can compare the studied population with the population behind the question they are asking.
Online stories can raise worthwhile questions. The research record decides how far an answer can responsibly go.
Bottom line
The STEP review places gastrointestinal effects at the center of its safety summary.1 Real-world percentages add detail but remain tied to their own samples.26 Small special-population records and one-patient reports can flag concerns without estimating general risk.4910 Product identity matters too, especially for a non-comparable biotherapeutic.12 For readers in the Philippines, the soundest approach is to ask for the denominator, design, participant profile, and exact product. A reassuring story and an alarming story require the same careful questions every time. Social posts can begin that inquiry; they cannot complete it.
Frequently asked questions
Which side effects appear most consistently in the selected research?
The STEP review identifies gastrointestinal symptoms as the most common side effects. It describes them as generally manageable and nonsevere.1 Retrospective cohorts in the United States, Türkiye, and a psychiatric setting also recorded gastrointestinal effects, although their populations and methods differed.2610
Does a 50.7% clinic rate apply to everyone?
No. The figure came from one retrospective US comparison involving 511 adults.2 The sample was 91.8% White and 74.8% female.5 It describes reported gastrointestinal symptoms within that dataset. The authors themselves called for research in more diverse populations.5
Are the oral and under-the-skin forms equally tolerable?
One 208-person retrospective preprint found no significant difference in gastrointestinal-symptom severity between the two forms.3 Dizziness was more frequent in the under-the-skin group.8 The study was not randomized, so it cannot establish identical tolerability across products, populations, or longer periods.3
What can a case report tell readers?
A case report can document an unusual clinical sequence in detail and alert researchers to a possible signal.4 The selected report involved one woman with several scan abnormalities after first semaglutide exposure.4 One observation cannot determine frequency, prove causation, or predict what typically happens.4
Why do the percentages differ between studies?
One study covered US obesity clinics and reported symptoms from one retrospective record.2 Another followed adults with type 2 diabetes in Türkiye for 30 weeks.6 A third used an explicitly non-comparable biotherapeutic without a control group.12 Their percentages belong to those separate settings.
How should readers in the Philippines judge local relevance?
Start with the country, setting, demographics, and event definition. The US cohort’s profile limits broad generalization.5 The Türkiye, UK, and Canadian records describe different groups.9610 Filipino readers should keep those differences attached to each imported percentage.
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Sources
Footnotes
-
Semaglutide in obesity and type 2 diabetes: A review of clinical trial evidence from 1 to 5 semaglutide treatment effect in people with obesity program.. Review of once-weekly semaglutide 2.4 mg trials in adults with overweight or obesity, including populations with and without type 2 diabetes. This is a review-level summary across several trials, not one universal event rate or a prediction for an individual. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13
-
Real-World Comparative Effectiveness of Tirzepatide and Semaglutide for Obesity: A Multicentered Study.. Adults prescribed semaglutide or tirzepatide for weight loss across multiple US health care centers from 2021 through 2024. The comparison was observational, and the reported percentages belong to this cohort rather than to all users. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
A Retrospective Study Evaluating the Efficacy and Safety of Oral Semaglutide Compared to Injectables in Controlling Diabetes and Weight Reduction. The cohort included 89 oral-form and 119 under-the-skin-form users with uncontrolled type 2 diabetes and obesity. The work was retrospective and a preprint, so it does not establish identical safety across products, populations, or longer follow-up. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
18 F-FDG PET/CT Five Days Post First Administration of Semaglutide : Side Effects in One Shot.. Single-patient PET/CT case report in which clinical evaluation supported suspected gastroparesis, cholecystitis, colitis, and possible acute kidney injury related to dehydration; symptoms resolved after supportive care and semaglutide withdrawal. A one-patient report can document a possible signal but cannot estimate frequency or establish causation for a wider population. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10
-
Real-World Comparative Effectiveness of Tirzepatide and Semaglutide for Obesity: A Multicentered Study.. Retrospective multicenter comparison of semaglutide and tirzepatide in US obesity care. The authors called for further studies in more diverse populations, so broad demographic generalization is limited. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Evaluation of the Efficacy of Semaglutide Dose Escalation in Reducing HbA1c Levels and Insulin Dose in Type 2 Diabetes Patients: Real-World Semaglutide Data from Türkiye, SEMA-TR Study.. Adults with type 2 diabetes in the Cukurova region were grouped by the maximum semaglutide amount recorded during follow-up. This was an observational grouping rather than a randomized safety comparison. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Evaluation of the Efficacy of Semaglutide Dose Escalation in Reducing HbA1c Levels and Insulin Dose in Type 2 Diabetes Patients: Real-World Semaglutide Data from Türkiye, SEMA-TR Study.. Thirty-week retrospective cohort of adults with type 2 diabetes. The abstract does not attribute every discontinuation to gastrointestinal effects or to any single reason. ↩ ↩2
-
A Retrospective Study Evaluating the Efficacy and Safety of Oral Semaglutide Compared to Injectables in Controlling Diabetes and Weight Reduction. Retrospective comparison of 89 oral-form and 119 under-the-skin-form users with type 2 diabetes and obesity. This was one preprint comparison and not a randomized head-to-head safety trial. ↩ ↩2
-
Efficacy and safety of semaglutide for obesity and hyperphagia in adults with Prader-Willi syndrome. Retrospective review of adults with Prader–Willi syndrome and overweight or obesity at a UK specialist clinic. The sample was very small, clinically specific, and reported in a preprint. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
The Effect of Semaglutide on Antipsychotic-Induced Weight Gain and Other Metabolic Parameters, among a Cohort of Inpatients.. Inpatients with severe mental illness who were receiving antipsychotic medicines at a Canadian center. The cohort was small, clinically specific, and had fewer participants available at later follow-up points. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Oral Health Considerations and Dental Management Guidelines for Semaglutide Medications.. Narrative review of semaglutide pharmacology, systemic effects, and possible oral manifestations relevant to dental care. The review describes possible secondary manifestations, not outcomes expected in every person. ↩ ↩2
-
Weight-Reduction and Safety Profile of Once-Weekly Non-Comparable Biotherapeutic Subcutaneous Semaglutide Among People With Obesity: A Real-World Retrospective Study.. Electronic records from 87 people with obesity across three urban private practices. The product was explicitly non-comparable, the study lacked a control group, and its figures should not be transferred to other products. ↩ ↩2 ↩3 ↩4