
TL;DR
-
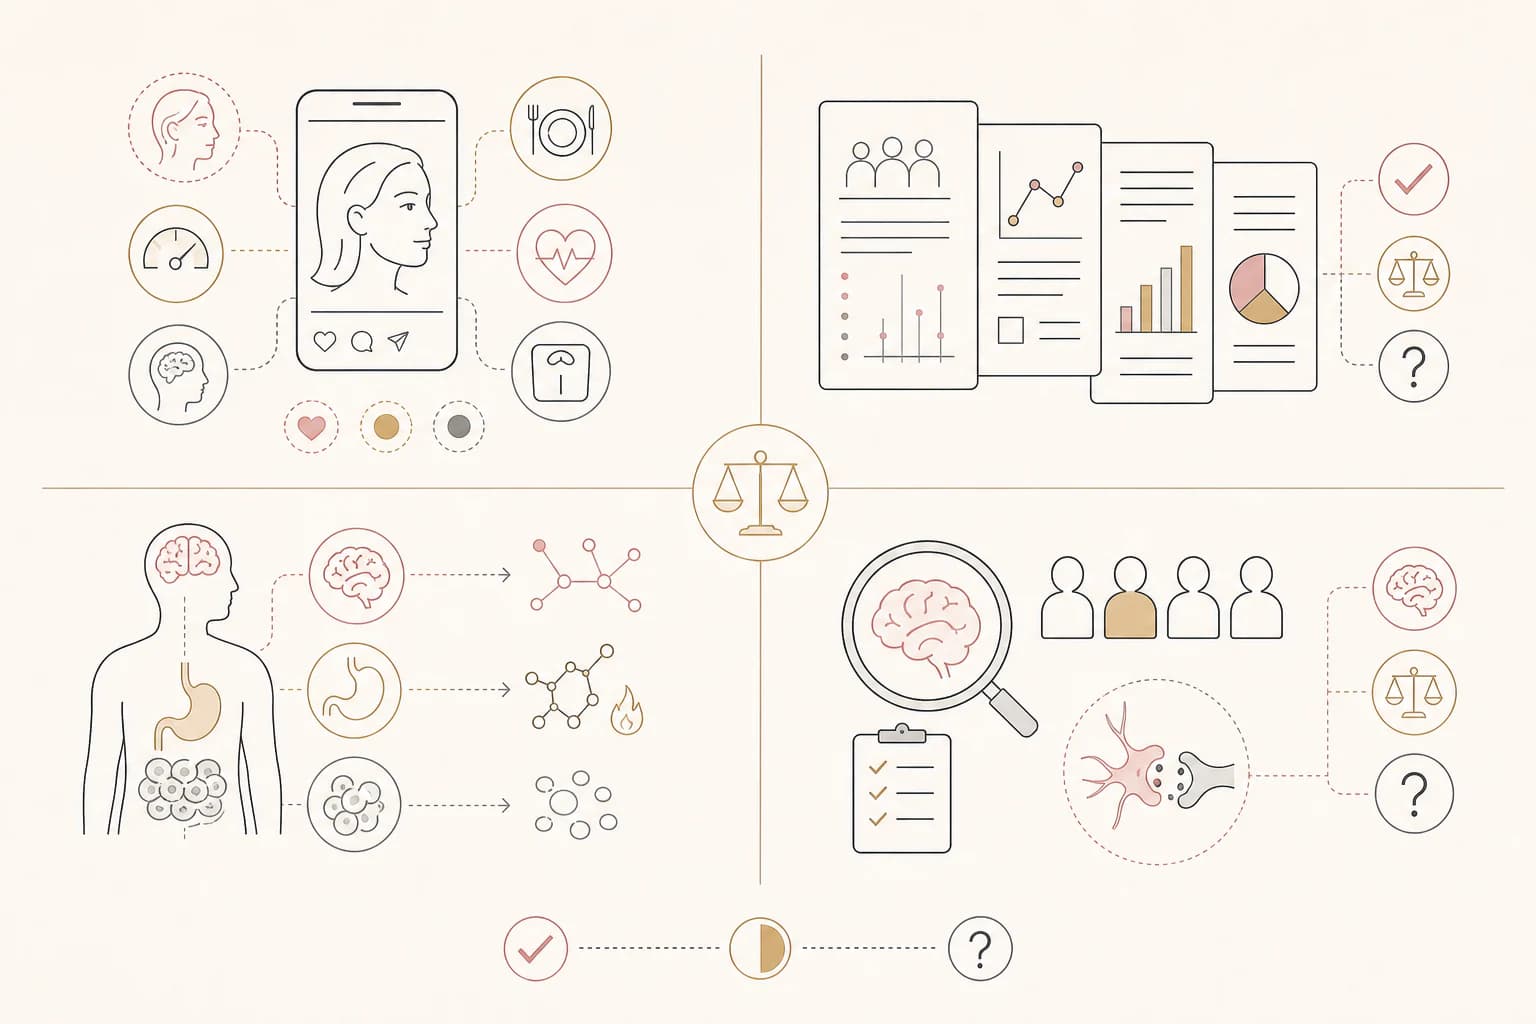
“Ozempic face” is a viral label, not a causal finding. The cited FDA record identifies one named semaglutide product, but it does not establish why someone’s face may look different or make a catalog item equivalent to that product.1
-
Metabolism is not one switch. Relevant studies measured mouse fat-tissue lipids, mouse body composition and muscle function, plus clinical measures in a small inpatient chart review. Those outcomes cannot be merged into one “metabolism boost” claim.2
-
Reward research is not the same as addiction evidence: one experiment studied healthy mice, while the human paper is a protocol for a planned cocaine-use-disorder trial rather than completed outcomes.3
-
A matched-record study found similar composite psychiatric risks for tirzepatide and semaglutide, yet its observational design cannot reproduce random assignment or predict one person’s experience.4
In the Philippines, phrases like “Ozempic face” can move from celebrity posts to group chats before the science catches up. The useful question is rarely whether a slogan is simply true or false. Ask what researchers measured, who or what they studied, and whether the paper reports findings or only a plan. Those details turn a dramatic headline into something readers can judge.
A myth is not yet a research question
“Ozempic face” sounds precise, but it does not define a measured facial outcome or its cause. The FDA source cited here is narrower: it records RYBELSUS semaglutide under one United States application, with an original approval date in 2019.1 That record applies to the named regulated product and indication, not to a catalog item.1 It also cannot assign a cause to an individual facial change.1 A useful causal study would need a defined feature, consistent timing, and a suitable comparison. It would also need to separate medicine exposure from weight change and other influences. Without those parts, the nickname remains an observation wrapped inside an explanation. It may start a conversation, but it should not finish one.
For readers looking for the exact topic, the Semaglutide card below opens its live catalog details. It is a catalog reference, not research evidence or a recommendation.
“Metabolism” covers several different measurements
A metabolic headline can refer to tissue molecules, blood markers, body composition, or energy use. The relevant papers did not measure a single shared “metabolism speed.”2 One experiment examined visceral fat from male mice with a type 2 diabetes model.5 Researchers reported differences in lipid classes, inflammatory markers, tissue features, and genes tied to lipid handling.5 Another mouse experiment tracked fat mass, lean mass, strength, and several organs.67 A human chart review instead recorded weight, HbA1c, and lipid measures in psychiatric inpatients.8 All belong under a broad metabolic umbrella, but each answers a narrower question.2 Calling them proof of a faster metabolism erases the endpoint, species, population, and study design that give each result meaning.
Body composition is more than one number
In a 14-week experiment, researchers studied mice with diet-induced obesity and several related modeled diseases.6 Semaglutide reduced fat mass by 31% and lean mass by 11% in that model.6 Those percentages describe the tested mice; they are not a forecast for people.6 Lean mass also is not identical to muscle strength or day-to-day function. The study assessed those outcomes separately.7 That distinction matters because a body-composition change does not automatically reveal its functional importance. It also prevents a common headline error: presenting any lean-mass reduction as a fixed human percentage. The careful reading is narrower. This animal experiment found changes in both fat and lean compartments under its own disease model, timeline, and laboratory conditions.6
Combination results stay with the combination
The same 14-week mouse study included semaglutide, exercise, combined treatment, and control groups.7 In the combined group, lean mass fell by 8% rather than 11% with semaglutide alone.67 Only the combined group significantly improved grip strength and gastrocnemius muscle-fiber diameter.7 Those findings belong to that specific exercise program, mouse model, and paired intervention.7 A separate three-week mouse experiment used a ketone-ester combination.9 It reported reduced lean mass and muscle performance with semaglutide alone, while the combination preserved those measures.9 That second result is also preclinical and combination-specific.9 It is not a human supplementation instruction. Across both experiments, the disciplined conclusion is about research design: a paired intervention cannot be credited to either component outside the tested setting.
Human records add context, not causal certainty
The human metabolic source is a retrospective review of 47 psychiatric inpatients.8 All had severe mental illness and were taking antipsychotic medicines, making this a specialized population.8 After semaglutide initiation, the charts showed changes in weight, HbA1c, and lipid measures.8 The review was small, uncontrolled, and observational.8 It therefore describes what happened in those records, not what semaglutide alone caused.8 The setting also limits broad generalization.8 Human clinical records also differ from controlled animal experiments.2 Mouse tissue studies can explore mechanisms in tightly managed conditions.5 Chart reviews can capture routine care, but other recorded and unrecorded factors travel with the result.8 Neither design supports a universal metabolism slogan.2
For readers comparing nearby catalog topics, the Tirzepatide card below opens its live catalog details. It is a separate catalog reference, not proof of equivalence, compatibility, or a recommendation.
Reward signals do not equal human addiction
One neuroscience paper studied healthy mice rather than people with a substance-use disorder.10 Semaglutide changed behavior in tests related to stress and reward pursuit.10 It also changed oscillatory activity in the nucleus accumbens across several frequency bands.10 These findings make the experiment relevant to reward circuitry, but they do not establish addiction outcomes in humans.10 Laboratory tasks and brain rhythms are not human craving, substance use, or recovery.10 Species and health status matter too.3 A healthy mouse experiment addresses a different question from research involving treatment-seeking adults.3 It can help researchers shape ideas about reward. It cannot support the broad social-media claim that semaglutide “switches off addiction” in people.103
The human addiction paper is a protocol
The human paper lays out a planned randomized, double-blind, placebo-controlled trial.11 It proposes enrolling 75 treatment-seeking adults with cocaine use disorder.11 Both groups would receive cognitive behavioral therapy, making semaglutide an adjunct in the planned design.11 Researchers intend to measure cue reactivity, cocaine demand, craving, self-reported use, and urine drug screens.12 Those endpoints are more directly connected to cocaine-use disorder than a healthy-mouse reward task.123 However, a protocol reports the question and methods, not the answer.1112 It provides no completed outcome to interpret.11 The accurate headline is therefore modest: researchers have specified how they plan to test the idea in humans, alongside behavioral therapy.
Psychiatric comparisons need an observational label
A separate retrospective study used a large federated health-record network.13 It compared adults with type 2 diabetes, obesity, or both who started tirzepatide, semaglutide, or another GLP-1 receptor agonist.13 Propensity-score matching balanced recorded demographic, clinical, and metabolic variables.13 After matching, tirzepatide and semaglutide had similar composite psychiatric risks in year-one and year-two analyses.4 Researchers flagged a nominal year-two anxiety difference for caution because they made multiple comparisons.4 Semaglutide was also associated with lower recorded risks for several psychiatric outcomes than earlier GLP-1 medicines during year one.14 These are comparative associations, not proof of protection or harm.1314 Matching strengthens a comparison, but it cannot account for every unrecorded difference or reproduce random assignment.13
Bottom line
Semaglutide myths mislead when they turn unlike research into one sweeping answer.23 The facial-change slogan lacks a defined causal outcome in the cited regulatory record.1 Metabolic papers here measure different endpoints across mice and a small inpatient review.2 Muscle findings are preclinical, and the strongest functional results belong to tested combinations.79 Reward behavior in healthy mice is not a human addiction outcome.10 The cocaine-use-disorder paper describes a planned trial, while psychiatric comparisons come from observational records.1113 Keep the species, population, endpoint, and study stage attached. That habit is more reliable than any viral verdict.
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Frequently asked questions
Is “Ozempic face” a diagnosis?
The phrase is a popular label, not a defined diagnosis in the cited FDA record.1 That record concerns one named RYBELSUS product and indication.1 Explaining a facial change would require a measured feature, timeline, comparison, and analysis of other influences.1 The nickname alone cannot establish cause.
Does semaglutide simply speed up metabolism?
The relevant studies measured different things: mouse fat-tissue lipids, mouse body composition and muscle function, plus clinical measures in a small inpatient chart review.2 None of those endpoints is a universal “metabolism speed.” The most accurate summary names the specific measurement, species, population, and design.
Do the muscle studies prove a human effect?
Both direct muscle experiments discussed here used mice.69 One ran for 14 weeks in a complex disease model, while the other ran for three weeks in obese, glucose-intolerant animals.69 Their lean-mass and function findings should remain preclinical, not become personal human forecasts.69
What do the exercise and ketone-ester findings mean?
They are results from two separate mouse combination experiments.79 Exercise accompanied semaglutide in one model, while a ketone ester accompanied it in another.79 Neither finding can be reassigned to a single component or turned into human guidance. The species, timeline, and paired intervention remain essential context.
Has semaglutide been shown to change cocaine addiction?
The human source is a protocol for a planned trial in treatment-seeking adults with cocaine use disorder.11 It lists craving, cue response, cocaine demand, self-report, and urine screens as intended outcomes.12 Because it is a protocol, it establishes planned methods rather than completed clinical results.11
What did the healthy-mouse reward study show?
Semaglutide changed stress- and reward-pursuit behavior and nucleus-accumbens rhythms in healthy mice.10 That makes it a preclinical clue about reward circuits.10 It does not demonstrate an addiction outcome in people.10 The experiment differs from the planned human trial in species, population, and endpoint.3
What did the psychiatric record study find?
Matched records showed similar composite psychiatric risks for tirzepatide and semaglutide across two analysis periods.4 Semaglutide also had lower recorded associations than earlier GLP-1 medicines for several year-one outcomes.14 Because the study was retrospective and observational, those comparisons do not prove protection, harm, or an individual result.1314
Sources
Footnotes
-
FDA Drugs@FDA record for OZEMPIC (ORAL SEMAGLUTIDE). Authoritative United States regulatory label for one named product. This product-specific record does not establish approval, equivalence, or facial effects for a catalog item. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Semaglutide Modulates Visceral Adipose Tissue Lipid Metabolism in Type 2 Diabetic Mice: A Lipidomics Study.; Semaglutide and Exercise Synergy in Obesity: Preserving Muscle Mass and Uncovering Organ Crosstalk.; The Effect of Semaglutide on Antipsychotic-Induced Weight Gain and Other Metabolic Parameters, among a Cohort of Inpatients.; Semaglutide-induced loss of skeletal muscle mass is blunted by co-administration of ketone esters.. Cross-study synthesis spanning preclinical experiments and observational human records. These endpoints cannot be collapsed into one claim that semaglutide simply speeds or slows metabolism. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Repurposing semaglutide as an adjunctive treatment for cocaine use disorder: protocol for a randomised controlled trial.; Semaglutide alters behaviour and nucleus accumbens oscillatory activity in healthy mice.. Cross-study synthesis of preclinical neuroscience and a human clinical-trial protocol. Neither source reports a completed human addiction outcome. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Neuropsychiatric Outcomes With Tirzepatide, Semaglutide, and Other GLP-1 Receptor Agonists.. Observational comparative-effectiveness analysis of matched health records. A nominal year-two anxiety difference was flagged for caution because of multiple comparisons. ↩ ↩2 ↩3 ↩4
-
Semaglutide Modulates Visceral Adipose Tissue Lipid Metabolism in Type 2 Diabetic Mice: A Lipidomics Study.. Preclinical mouse tissue, histology, lipidomics, and gene-expression experiment. Mouse tissue remodeling is not a measurement of a universal human metabolic rate. ↩ ↩2 ↩3
-
Semaglutide and Exercise Synergy in Obesity: Preserving Muscle Mass and Uncovering Organ Crosstalk.. Preclinical animal experiment in Ldlr-/-.Leiden mice with multiple modeled diseases. The percentages are model-specific and cannot be presented as expected human outcomes. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Semaglutide and Exercise Synergy in Obesity: Preserving Muscle Mass and Uncovering Organ Crosstalk.. Preclinical combination arm within a 14-week mouse experiment. The result belongs to the tested species, disease model, exercise program, and combination. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
The Effect of Semaglutide on Antipsychotic-Induced Weight Gain and Other Metabolic Parameters, among a Cohort of Inpatients.. Small observational human chart review in a specialized inpatient population. Without randomization or a control group, the review describes associations rather than causal effects. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Semaglutide-induced loss of skeletal muscle mass is blunted by co-administration of ketone esters.. Short preclinical mouse experiment with monotherapy and combination groups. The combination finding is not human evidence and is not a supplementation recommendation. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Semaglutide alters behaviour and nucleus accumbens oscillatory activity in healthy mice.. Preclinical neuroscience experiment in healthy, non-diseased mice. Behavioral tests and brain rhythms in healthy mice do not establish addiction outcomes in people. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10
-
Repurposing semaglutide as an adjunctive treatment for cocaine use disorder: protocol for a randomised controlled trial.. Human clinical-trial protocol describing planned research rather than findings. A protocol establishes the planned design but cannot establish effectiveness or safety outcomes. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
Repurposing semaglutide as an adjunctive treatment for cocaine use disorder: protocol for a randomised controlled trial.. Prespecified measurements in a planned human randomized trial. These are intended measurements, not reported results. ↩ ↩2 ↩3 ↩4
-
Neuropsychiatric Outcomes With Tirzepatide, Semaglutide, and Other GLP-1 Receptor Agonists.. Large observational study using federated routine-care health records. Matching can balance recorded variables but cannot reproduce random assignment. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Neuropsychiatric Outcomes With Tirzepatide, Semaglutide, and Other GLP-1 Receptor Agonists.. Observational propensity-matched health-record comparison. The associations do not prove that semaglutide caused protection or changed any individual's risk. ↩ ↩2 ↩3 ↩4