TL;DR
- A scar is the end of several overlapping repair phases, so one collagen or inflammation result cannot describe the final appearance of human skin.1
- KPV improved re-epithelialization in injured rabbit corneas, but that model did not measure scar appearance on human facial skin.2
- GHK-Cu increased matrix components in one rat wound model, while another rat model found no significant change in its main measures.3
- A GHK-Cu human study reported better diabetic-ulcer outcomes, yet an ulcer result is not proof of fading or preventing an aesthetic scar.4
For Filipino readers sorting through skin-repair promises, the hard part is rarely the scientific vocabulary. The challenge is keeping each result attached to its own model and outcome. Those boundaries genuinely matter. This guide also explains how Philippine promotion rules sharpen the questions worth asking before research becomes sales copy.
A scar claim contains several different questions
Skin repair is not one switch turning on.1 It moves through overlapping inflammatory, proliferative, and remodeling phases.1 Keratinocytes rebuild the surface, while fibroblasts help form and reorganize the supporting matrix beneath it.1 Blood-vessel growth and collagen change are other parts of the same process.1
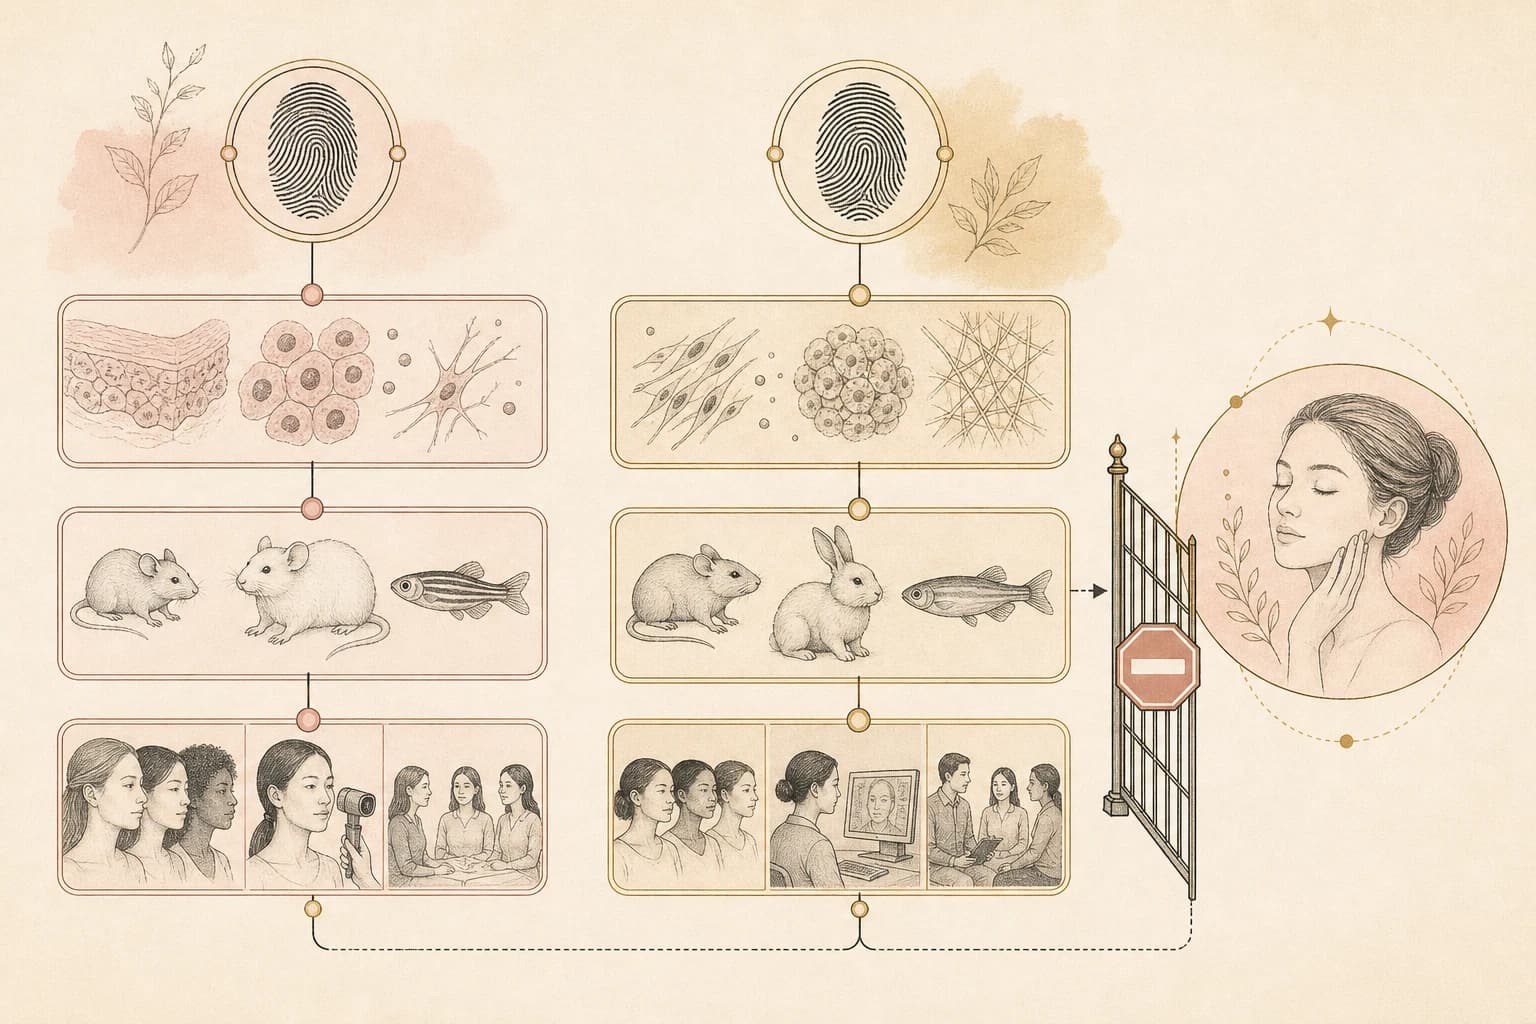
A change in inflammation does not report the final scar.1 More collagen does not automatically mean a smoother result.1 Faster surface closure also differs from long-term color, height, texture, or comfort.1 A useful reading therefore starts with four labels: model, tissue, measurement, and follow-up. Only then should the finding be connected to the claim being made.
KPV is named here only to introduce the following neutral catalog reference.
KPV is short, but its name still needs precision
KPV is a three-amino-acid peptide: lysine, proline, and valine.5 The short name can hide an important chemistry detail.5 The free-base and acetate forms are distinct bulk drug substances in the U.S. FDA assessment.5 The agency also found inconsistent naming around materials called KPV.5
For a reader, this creates a basic identity question before any skin claim is considered. Does the cited paper study the same form named in the promotional material? A shared nickname cannot answer that by itself.5 The FDA review also treated identity, purity, impurities, and microbiological controls as separate product-characterization issues.6 None of those issues can be resolved by a before-and-after photograph. They require records about the exact substance and finished formulation.6
The same review found the evaluated information inadequate to determine KPV effectiveness for its nominated wound and inflammatory uses.7 That was a U.S. compounding assessment, not a Philippine product decision.7
The closest KPV repair result is still not a skin-scar trial
One KPV experiment removed the surface epithelium from rabbit corneas.2 Treated eyes had smaller remaining defects and reached complete re-epithelialization earlier than vehicle-treated eyes.2 Cultured rabbit corneal cells were also part of the research.2
This is a positive result within its model.2 It is also easy to overextend. The cornea is eye tissue, the subjects were rabbits, and the outcome was surface closure.2 The experiment did not measure the appearance of an acne scar, surgical scar, burn scar, or keloid on a person.2 It therefore supports a narrow sentence about rabbit corneal repair, not a broad human aesthetic promise.
That distinction is not dismissive. It preserves what the experiment actually found while keeping a different consumer question open.
Reaching prepared skin is different from repairing it
A separate KPV study used dermatomed human skin outside the body.8 With passive diffusion, permeation stayed below the experiment’s detection limit.8 Microneedles and iontophoresis increased measured delivery and retention through the prepared skin.8
This study answers a formulation question: could researchers move measurable KPV across a skin barrier under laboratory conditions?8 It does not answer whether a living person’s wound closes, whether a mature scar changes, or whether exposure is safe.8 Those are different endpoints.
The delivery methods also matter because the result cannot be assigned to KPV alone.8 The measured change occurred when the barrier was altered or an electrical method was used.8 A claim about passive cosmetic application would therefore need its own matching evidence.
GHK-Cu has several signals, not one simple verdict
GHK-Cu combines the tripeptide glycyl-histidyl-lysine with copper in the cited wound research.3 In rat wound chambers, it produced concentration-dependent increases in collagen, total protein, DNA, and glycosaminoglycans.3 These measures describe material accumulating in an experimental wound space.3
Another study examined cultured dermal fibroblasts.9 GHK-Cu increased MMP-2 expression and secretion, along with secretion of TIMP-1 and TIMP-2.9 These molecules take part in matrix-remodeling activity within that cell model.9 The finding is not a photograph of a healed scar or a report from a participant.9
Together, the papers support specific biological observations.3 They do not create a direct aesthetic result. “More collagen” and “more remodeling signals” are measurements, not synonyms for a less visible scar.9
A negative animal result belongs beside the positive one
Not every GHK-Cu animal model pointed in the same direction. Researchers tested a topical gel on irradiated rat dorsal flaps for ten days.10 Under the study’s statistical threshold, GHK-Cu did not significantly change ischemic area, blood-vessel count or area, or VEGF expression compared with control.10
This result does not cancel the rat wound-chamber findings.10 The injury model, formulation, endpoints, and experimental setting were different.10
That is an important magazine-reading habit: keep a negative result in its original frame, just as with a positive result. Neither should be stretched into a universal verdict. The fairest summary names what changed, what did not, and where each test happened.
GHK-Cu is named here only to introduce the following neutral catalog reference.
Human ulcer evidence is not an aesthetic-scar result
A randomized, evaluator-blinded study tested a topical GHK-Cu complex in people with diabetic neuropathic ulcers.4 Both groups also received standardized wound care.4 The report found greater plantar-ulcer closure and fewer infections with the GHK-Cu complex than with vehicle.4
That is directly relevant human wound evidence.4 Its limits are equally direct. A chronic diabetic foot ulcer is not a mature acne mark, surgical scar, or keloid.4 Wound closure and infection are not measurements of scar fading or cosmetic texture.4
A newer ClinicalTrials.gov record describes a recruiting phase 2 study of GHK-Cu gel on standardized acute skin wounds in healthy adults.11 It plans to measure closure, symptoms, scar quality, and safety.11 The registry documents the study design, not a positive result.11
Philippine rules sharpen the consumer question
Philippine FDA rules say an unauthorized health product must not be advertised or promoted.12 They also say promotional claims must stay within the approved label or other FDA approval.12 Those are general national rules, not a finding about either catalog entry.
For a Filipino reader, the practical question is therefore more exact than “Is there a paper?” A paper may discuss rabbit corneas, rat wounds, cultured cells, or diabetic ulcers.2 The claim in front of you may promise something else entirely. The product identity, authorized wording, and cited endpoint must still match.12
This approach avoids two shortcuts. Research language does not automatically make an ad compliant.12 A regulatory rule also does not tell us that every product sharing a peptide name has the same identity, quality, or evidence.5
Bottom line
KPV and GHK-Cu sit inside a complicated repair story, not a single scar switch.1 KPV has a positive rabbit-corneal result and a laboratory skin-delivery study, but neither reports human aesthetic scar change.2 GHK-Cu changed matrix measures in rat wounds and fibroblast cultures, yet another rat model found no significant change in its main endpoints.10 Its human ulcer result remains tied to diabetic wounds and standardized care.4
For readers in the Philippines, the sound approach is to match the exact substance, model, endpoint, and authorized claim.12 A study can be interesting without becoming a catalog promise. Do not erase the boundary between the paper and the pitch.
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Frequently asked questions
What is the difference between wound closure and scar repair?
Wound closure describes rebuilding a surface after injury, while scar formation continues through matrix and collagen remodeling.1 A study can report earlier surface closure without measuring later color, height, texture, or comfort.1 The endpoint named in the paper should therefore stay attached to the claim.
Did KPV improve a human skin scar?
The cited positive KPV repair experiment involved mechanically injured rabbit corneas.2 It measured epithelial defect size and re-epithelialization, not human scar appearance.2 The separate human-skin experiment studied delivery through excised tissue, so it did not report a living participant’s scar outcome.8
Why does the form of KPV matter?
The U.S. FDA assessment distinguishes KPV free base from KPV acetate as separate bulk drug substances.5 It also describes inconsistent naming around KPV materials.5 A short ingredient label therefore cannot establish that a promoted material matches the exact substance used in a cited experiment.
What did the GHK-Cu rat studies report?
One rat wound-chamber experiment found concentration-dependent increases in several matrix measures, including collagen.3 A different irradiated-flap experiment found no significant change in its ischemia, blood-vessel, or VEGF measures.10 Each result belongs to its own injury model and endpoints.
Does the diabetic-ulcer study prove a cosmetic scar claim?
No. The human study concerned diabetic neuropathic ulcers and reported wound-closure and infection outcomes alongside standardized care.4 Those findings should remain connected to that medical wound context.4 They do not directly measure whether an acne mark, surgical scar, or keloid becomes less visible.
What should Filipino readers check in a promotion?
Start with the exact product identity and the exact wording being promoted. Philippine FDA rules restrict health-product advertising and require claims to stay within approved wording.12 Then compare the ad’s promise with the paper’s model and endpoint, because a rat wound or ulcer result may answer another question.
Sources
Footnotes
-
Cutaneous Wound Healing: An Update from Physiopathology to Current Therapies. Peer-reviewed review of normal cutaneous wound-healing biology. A change in one phase or laboratory marker does not by itself establish the final appearance or behavior of a human scar. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
Effects of the COOH-terminal tripeptide alpha-MSH(11-13) on corneal epithelial wound healing: role of nitric oxide. Animal experiment in rabbit eyes, paired with cultured rabbit corneal epithelial cells. A rabbit corneal surface is not human facial skin, and re-epithelialization is not the same endpoint as aesthetic scar appearance. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
In vivo stimulation of connective tissue accumulation by the tripeptide-copper complex glycyl-L-histidyl-L-lysine-Cu2+ in rat experimental wounds. Animal wound-chamber experiment with local GHK-Cu exposure and biochemical tissue measurements. More matrix material in a rat wound chamber does not establish a better-looking or clinically improved human scar. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Enhanced healing of ulcers in patients with diabetes by topical treatment with glycyl-L-histidyl-L-lysine copper. Multicenter controlled clinical study in patients with diabetic neuropathic ulcers. A chronic diabetic ulcer is not an aesthetic scar, and the study does not establish scar fading or cosmetic skin repair. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10
-
FDA Evaluation of KPV-Related Bulk Drug Substances (KPV (Free Base) and KPV Acetate). 2026 U.S. FDA evaluation of KPV free base and KPV acetate for the 503A bulk drug substances list. The U.S. assessment does not describe a specific Philippine catalog item or determine Philippine regulatory status. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
FDA Evaluation of KPV-Related Bulk Drug Substances (KPV (Free Base) and KPV Acetate). Regulatory assessment of KPV-related bulk drug substances and proposed compounded products. These are U.S. compounding-assessment concerns, not findings about the quality or safety of any named catalog product. ↩ ↩2
-
FDA Evaluation of KPV-Related Bulk Drug Substances (KPV (Free Base) and KPV Acetate). Regulatory review of submitted references and the agency's searches for the nominated compounding uses. This conclusion is limited to the U.S. 503A evaluation and should not be turned into an exhaustive claim about every possible study or jurisdiction. ↩ ↩2
-
Transdermal Iontophoretic Delivery of Lysine-Proline-Valine (KPV) Peptide Across Microporated Human Skin. Laboratory transdermal-delivery experiment using excised human skin. The study measured delivery through prepared skin, not scar repair, clinical benefit, or safety in a living person. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8
-
The tripeptide-copper complex glycyl-L-histidyl-L-lysine-Cu2+ stimulates matrix metalloproteinase-2 expression by fibroblast cultures. Laboratory study of extracellular-matrix remodeling signals in fibroblast cultures. A cell-culture marker does not report wound closure, scar appearance, or a participant outcome. ↩ ↩2 ↩3 ↩4 ↩5
-
Effects of topical copper tripeptide complex on wound healing in an irradiated rat model. Ten-day controlled animal study of irradiated dorsal rat flaps. The negative result belongs to this specific animal injury model and does not erase different findings from other models. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Topical GHK-Cu Gel for Acute Skin Wound Healing (CuHeal). Current U.S. clinical-trial registry record with planned wound and scar measurements. A registry entry documents a study plan and recruitment status; it does not demonstrate a positive outcome. ↩ ↩2 ↩3
-
Rules and Regulations Implementing Republic Act No. 9711. Philippine Department of Health rules implementing Republic Act No. 9711. This general rule does not establish the registration, approval, legality, availability, or quality of any specific product. ↩ ↩2 ↩3 ↩4 ↩5 ↩6