Quick answer
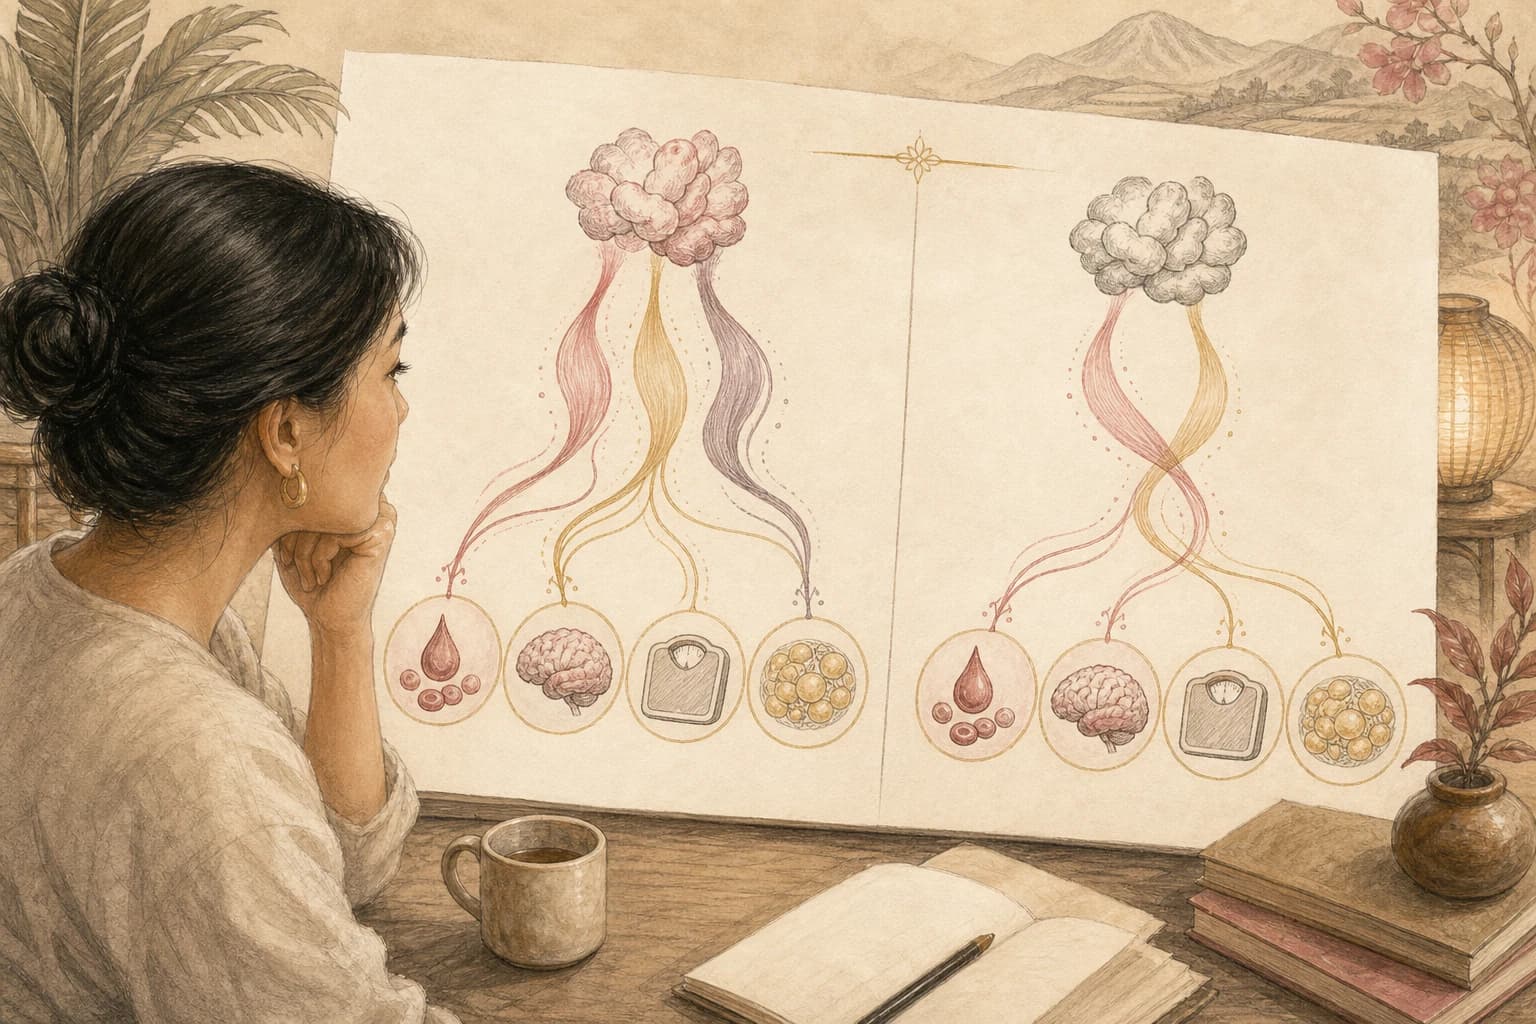
Retatrutide is called a triple agonist because it targets GIP, GLP-1, and glucagon receptors; tirzepatide is a dual agonist for GIP and GLP-1 receptors. That extra pathway makes the research programs biologically different, but it does not prove that “three is better than two.” The reported retatrutide results come from its own diabetes, appetite, and body-composition studies. Without a suitable randomized head-to-head trial, comparing headline percentages across separate programs can mislead Filipino readers.1234
What do “triple” and “dual” agonist mean?
An agonist activates a receptor and influences the signals linked with it. Retatrutide was designed to act at three receptor families: GIP, GLP-1, and glucagon.
Tirzepatide acts at GIP and GLP-1 receptors. This is why articles use “triple agonist” for retatrutide and “dual agonist” for tirzepatide.
The labels describe pharmacology, not a score. A third target can change effects, side effects, exposure response, and the population best suited for research.
It can also make interpretation harder. Researchers must learn how the combined signal behaves rather than adding three separate textbook descriptions.
More receptor activity is not automatically more useful. The meaningful comparison is the balance of measured benefits, harms, and certainty over time.
Readers researching Retatrutide can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
What has retatrutide shown in human trials?
In a randomized phase 3 trial of adults with type 2 diabetes, retatrutide lowered HbA1c more than placebo over 40 weeks.1
The same trial also reported greater body-weight reduction than placebo.2 Those results establish differences within that trial, not superiority over tirzepatide.
The population had type 2 diabetes that was inadequately controlled with diet and exercise alone. That context matters when someone tries to generalize the result.
A phase 2 exploratory analysis found larger reductions in self-reported appetite, hunger, and prospective food consumption than placebo.3
Higher retatrutide groups also showed stronger changes in perceived hunger and disinhibition, while differences from dulaglutide were less consistent.5
These were questionnaires, not direct measurements of every meal. They help describe the experience but cannot prove how much an individual ate.
What does the body-composition research add?
A phase 2 DXA substudy reported greater total fat-mass reduction with retatrutide than comparator groups among adults with type 2 diabetes.4
DXA estimates fat, lean soft tissue, and bone mineral. It provides more detail than a scale, but its result still belongs to the tested group and follow-up.
A fat-mass finding does not reveal every aspect of health. Strength, function, symptoms, blood markers, and adverse events remain separate questions.
Nor does it prove that the same proportion will appear in a different trial. Starting weight, diabetes status, treatment length, and participant retention can change averages.
The correct conclusion is narrow: retatrutide reduced fat mass in that substudy. “Triple agonism melts only fat” would be an unsupported upgrade.
Why can’t separate trial percentages be ranked?
Imagine two races held on different courses, in different weather, with different runners. The finish times are real, but comparing them does not identify the faster athlete with confidence.
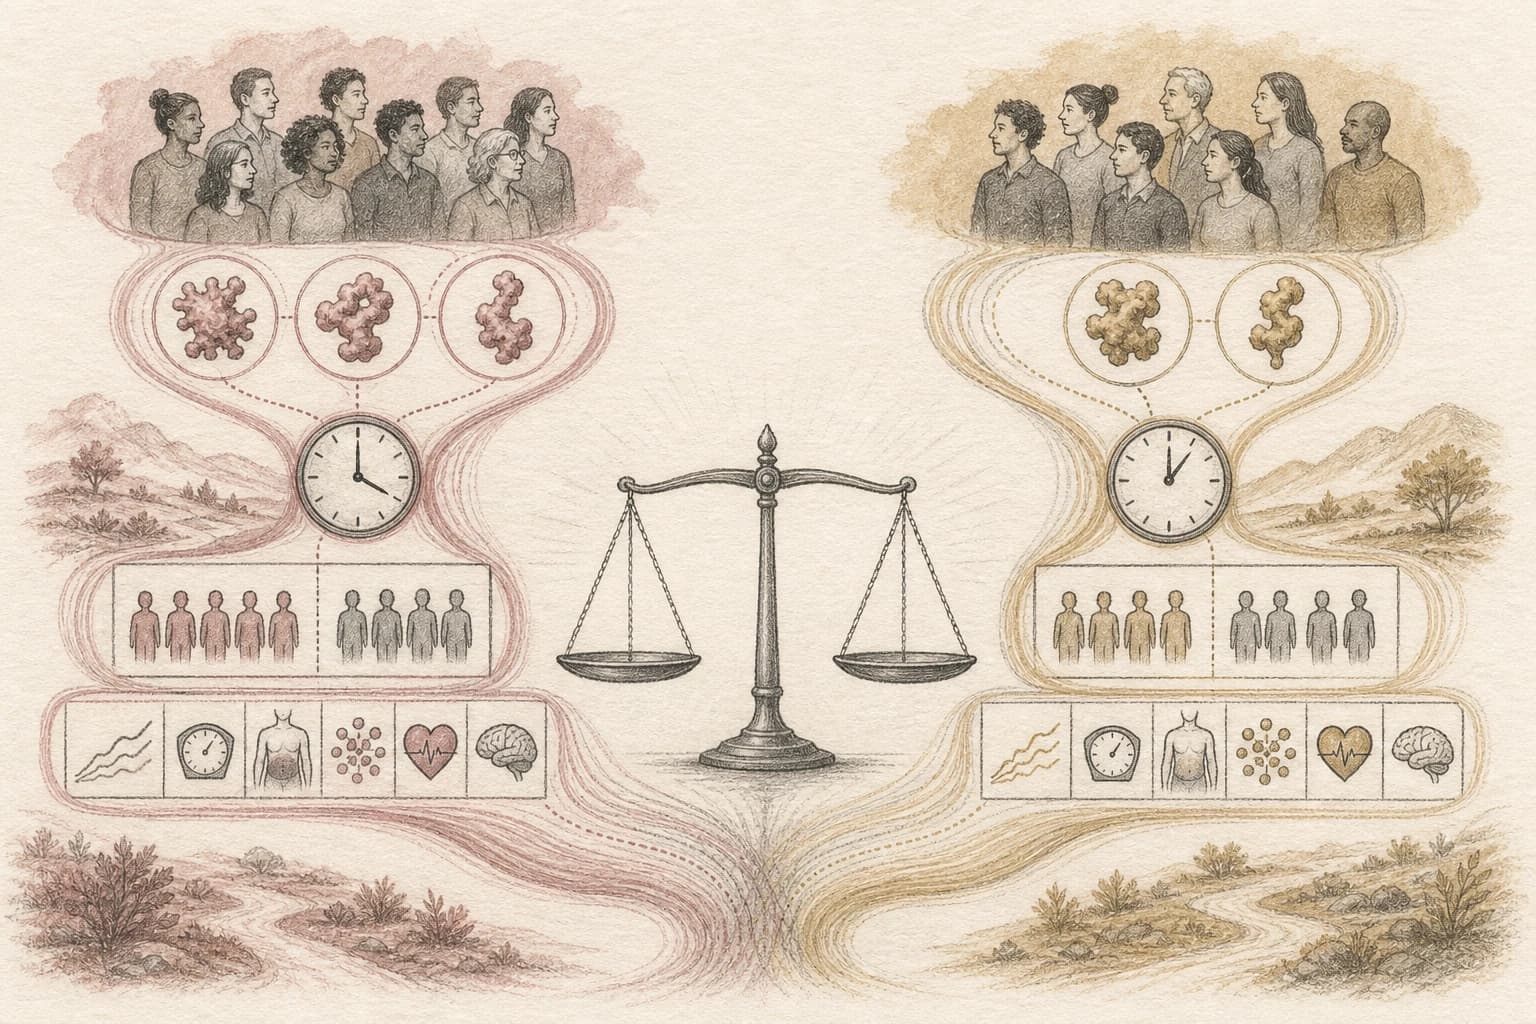
Separate drug trials can differ in participant health, starting weight, lifestyle support, follow-up, missing data, and statistical methods.
The chosen study groups and treatment duration also matter. Taking the largest number from each program encourages cherry-picking.
A direct head-to-head trial uses the same eligibility rules, sites, schedule, endpoints, and analysis plan. Random assignment reduces systematic differences between groups.
Even then, “better” needs a definition. Greater average weight change might come with different tolerability, discontinuation, access, or long-term uncertainty.
Without that design, receptor counting and cross-trial percentages are clues—not a verdict.
Publication timing creates another trap. A newer compound can have fewer completed studies simply because its program started later. That does not make its early result weaker or stronger by default. It means the uncertainty is shaped differently. Mature evidence offers more repetition and longer observation; emerging evidence may answer newer questions but leave wider gaps. A fair comparison shows both the result and the amount of history behind it.
What should a fair comparison include?
First, name the exact endpoint. HbA1c, body weight, appetite score, and fat mass are not interchangeable.134
Second, show the population. Results in adults with type 2 diabetes cannot silently become universal outcomes.
Third, report the comparator. A placebo difference and an active-drug difference answer different questions.
Fourth, include side effects, withdrawals, and missing follow-up. A headline average can look stronger when people who stopped are hard to see.
Finally, separate regulatory status from research excitement. An official medicine record for tirzepatide does not transfer to retatrutide, and an active research program is not the same as a Philippine product record.
What should Filipino readers verify?
The Philippine FDA Verification Portal separates licensed establishments from registered or notified products.6 Search the exact item, not just the company offering it.
Compare name, manufacturer, dosage form, and current authorization. Similar labels and pathway descriptions do not establish identical products.
WHO notes that falsified medical products can look convincing and may require laboratory analysis.7 A sealed box or polished listing is not chemical authentication.
This is especially important when two names trend together. Sellers may encourage readers to treat “dual” and “triple” as shopping tiers rather than different evidence programs.
A careful review keeps the trial result, molecule identity, and local record separate until each is verified.8
How can a comparison headline be audited?
Ask whether both compounds were tested in the same randomized trial. If not, the article should avoid a winner.
Find the exact numbers and their denominators. A percentage without the starting value or time point can conceal more than it reveals.
Check whether the outcome was prespecified or exploratory. Appetite analyses can be informative without carrying the same role as a primary endpoint.3
Look for the less exciting results too. An honest comparison does not select only the most favorable experimental amount, subgroup, or measurement.
The best answer may remain “not known.” That is more accurate than turning receptor arithmetic into clinical certainty.
Readers comparing this topic with Tirzepatide can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
Bottom line
Retatrutide and tirzepatide are not simply three-versus-two versions of the same product. Retatrutide’s phase 3 and phase 2 research reports changes in HbA1c, body weight, appetite measures, and fat mass. Those findings are meaningful inside their own studies, but they do not prove superiority over tirzepatide.
A dependable comparison needs a suitable randomized head-to-head design, common endpoints, adequate follow-up, and balanced safety reporting. Filipino readers should also confirm exact local product records rather than treating research status as authorization. Receptor count explains the scientific idea; it does not choose a winner.
Frequently asked questions
What makes retatrutide a triple agonist?
It acts at GIP, GLP-1, and glucagon receptors.
What makes tirzepatide a dual agonist?
It acts at GIP and GLP-1 receptors.
Did the cited retatrutide trial compare it directly with tirzepatide?
No. Its phase 3 comparison was with placebo.12
Does more receptor activity mean better results?
No. Outcomes, harms, population, and evidence quality must be measured.
Do the two catalog cards suggest combining the products?
No. They are separate catalog references, not a suggested combination.
Sources
Footnotes
-
Efficacy and safety of retatrutide, a GIP, GLP-1, and glucagon receptor agonist, in people with type 2 diabetes and inadequate glycaemic control with diet and exercise (TRANSCEND-T2D-1): a double-blind, randomised, phase 3 trial.. Randomized, double-blind, placebo-controlled phase 3 trial in adults with type 2 diabetes inadequately controlled by diet and exercise alone. The abstract reports trial findings but the supplied excerpt does not include the full numerical detail. ↩ ↩2 ↩3 ↩4
-
Efficacy and safety of retatrutide, a GIP, GLP-1, and glucagon receptor agonist, in people with type 2 diabetes and inadequate glycaemic control with diet and exercise (TRANSCEND-T2D-1): a double-blind, randomised, phase 3 trial.. Key secondary endpoint in the phase 3 diabetes trial. This is a trial result, not evidence of superiority over tirzepatide. ↩ ↩2 ↩3
-
Appetite, eating attitudes, and eating behaviours during treatment with retatrutide in adults with type 2 diabetes: Results of a phase 2 study.. Pre-specified exploratory analyses of self-reported appetite and eating-behavior measures. These were patient-reported outcomes, not direct measures of calorie intake. ↩ ↩2 ↩3 ↩4
-
Effects of retatrutide on body composition in people with type 2 diabetes: a substudy of a phase 2, double-blind, parallel-group, placebo-controlled, randomised trial.. DXA-based substudy in adults with type 2 diabetes. The abstract excerpt does not provide the full comparative values in the supplied metadata. ↩ ↩2 ↩3
-
Appetite, eating attitudes, and eating behaviours during treatment with retatrutide in adults with type 2 diabetes: Results of a phase 2 study.. Exploratory eating-behavior analysis within a phase 2 trial. The abstract says differences versus dulaglutide were less consistent. ↩
-
Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Official Philippine regulatory verification service. A portal record applies to the exact product or establishment named in that record. ↩
-
WHO laboratory analysis of suspected falsified medical products; WHO laboratory testing for health-product regulation. WHO guidance on suspected falsified medical products and regulatory laboratory testing. Appearance alone cannot authenticate a product or establish a research outcome. ↩
-
Efficacy and safety of retatrutide, a GIP, GLP-1, and glucagon receptor agonist, in people with type 2 diabetes and inadequate glycaemic control with diet and exercise (TRANSCEND-T2D-1): a double-blind, randomised, phase 3 trial.; Appetite, eating attitudes, and eating behaviours during treatment with retatrutide in adults with type 2 diabetes: Results of a phase 2 study.; Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Editorial synthesis of the canonical research records and Philippine verification sources. This synthesis is educational and is not personal medical advice or a product recommendation. ↩


