
Quick answer
Oral and injectable semaglutide contain the same active molecule, but readers should not treat every result as interchangeable. Formulation, route, schedule, population, and trial design all shape what a study can show.
Oral semaglutide has its own cardiovascular evidence, while weekly injectable semaglutide has a larger set of comparison trials in type 2 diabetes. A new oral-film experiment involved minipigs, not people. For Filipino readers, the exact local product and establishment record matters just as much as the familiar ingredient name.12345
What stays the same between the two forms?
Semaglutide is the active ingredient named in both oral and injectable research. Both forms are studied through the GLP-1 receptor pathway, so they belong to the same broad medicine family.
That shared identity does not erase formulation differences. A tablet must move through the digestive system and reach circulation, while an delivered non-orally formulation enters by another route.
Researchers therefore test each form with its own schedule, comparator, and outcome plan. A result follows the exact intervention studied, not simply the ingredient name printed in a headline.
The FDA record for the oral product Rybelsus identifies semaglutide and a specific United States application.6 It does not prove that an unnamed online item is the same product.
The practical rule is simple: keep the molecule, form, official product name, and evidence together. If one of those details changes, recheck the source before carrying over a conclusion.
Readers researching Semaglutide can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
What does oral semaglutide evidence show?
The SOUL program supplies direct cardiovascular evidence for oral semaglutide in a defined high-risk population.
A post hoc analysis described 9,650 adults aged 50 or older with type 2 diabetes and cardiovascular disease, chronic kidney disease, or both. Median follow-up was 47.5 months.1
The trial reported a 14 percent lower risk for its three-part cardiovascular endpoint with oral semaglutide.1 That endpoint combined cardiovascular death, nonfatal heart attack, and nonfatal stroke.
This is a clinical outcome, not merely a change in blood sugar or body weight. It is also population-specific. It does not automatically establish the same effect for younger adults, people without diabetes, or every semaglutide form.
A review reported that oral semaglutide met cardiovascular non-inferiority criteria in PIONEER 6.2 Non-inferiority asks whether a treatment avoids being unacceptably worse than its comparator.
The same review reported no significant reduction in SOUL’s major kidney outcome.7 That finding should remain tied to the named endpoint rather than becoming a broad claim that semaglutide does or does not affect every kidney measure.
What does injectable semaglutide evidence add?
Weekly injectable semaglutide has been compared with several injectable diabetes treatments, but that is not the same as a direct oral-versus-injectable trial.
A meta-analysis assembled four SUSTAIN randomized trials with 3,680 participants whose type 2 diabetes was not controlled by oral medicines alone.4
The review compared weekly semaglutide with basal insulin or other GLP-1 receptor agonists. It reported differences in HbA1c, body weight, blood pressure, gastrointestinal events, and treatment discontinuation.
Several findings carried low certainty because the trials differed, used open-label designs, and were sponsored by the manufacturer.4 Those limitations do not erase the results, but they affect how confidently readers should generalize them.
Most importantly, the meta-analysis did not compare injectable semaglutide directly with oral semaglutide.4 It cannot rank the two forms as if they were tested side by side under one protocol.
A route comparison needs matched populations, experimental amounts, follow-up, endpoints, and analysis. Without that structure, apparent differences may come from trial design rather than the formulation itself.
Can study results be compared across formulations?
Cross-trial comparisons can offer clues, but they are weaker than a well-designed direct comparison.
One analysis compared injectable tirzepatide with oral semaglutide by statistically adjusting results from separate obesity trials.6 The authors clearly described it as an indirect comparison.
That example shows why labels matter. An indirect analysis relies on assumptions about whether the original trial populations and measurements can be aligned.
It cannot reproduce random assignment between oral and injectable semaglutide. Nor can it remove every difference in adherence, timing, background care, or missing data.
Readers should also separate convenience from effectiveness. A preferred route may influence whether someone follows a schedule, but preference alone does not prove a better clinical outcome.
The fairest comparison names the form, exposure strategy, population, comparator, duration, and outcome. A single ingredient name is not enough information.
Readers comparing this topic with Tirzepatide can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
What does the oral-film experiment really tell us?
A newer delivery experiment tested a semaglutide thin film designed for use under the tongue.
The study involved 40 female, non-diabetic, non-obese Göttingen minipigs. Researchers compared the film with an oral tablet, an under-the-skin form, and placebo over eight weeks, followed by one week of observation.3
That makes it preclinical evidence. It can help researchers ask whether a delivery platform deserves further development.
It cannot establish human safety, effectiveness, product equivalence, or Philippine authorization.3 Minipig results should not be presented as if Filipino patients had already been tested.
The film also should not be confused with every oral semaglutide product. Different formulation technology can change absorption and exposure, even when the active molecule has the same name.
This is a useful example of evidence boundaries. A delivery idea can look early-stage while still being far from a verified, locally authorized health product.
What should Filipino readers verify?
Begin with the exact product rather than a social-media label such as “oral Ozempic” or “semaglutide drops.”
The Philippine FDA Verification Portal separates licensed establishments from registered or notified health products.5 Search the exact spelling, then compare the listed form, company, and authorization details.
A licensed seller record and a registered product record answer different questions. Finding one does not automatically prove the other.
WHO warns that some falsified medical products can closely resemble genuine items and may require quality-control analysis.8 Packaging photographs or a familiar logo cannot establish contents.
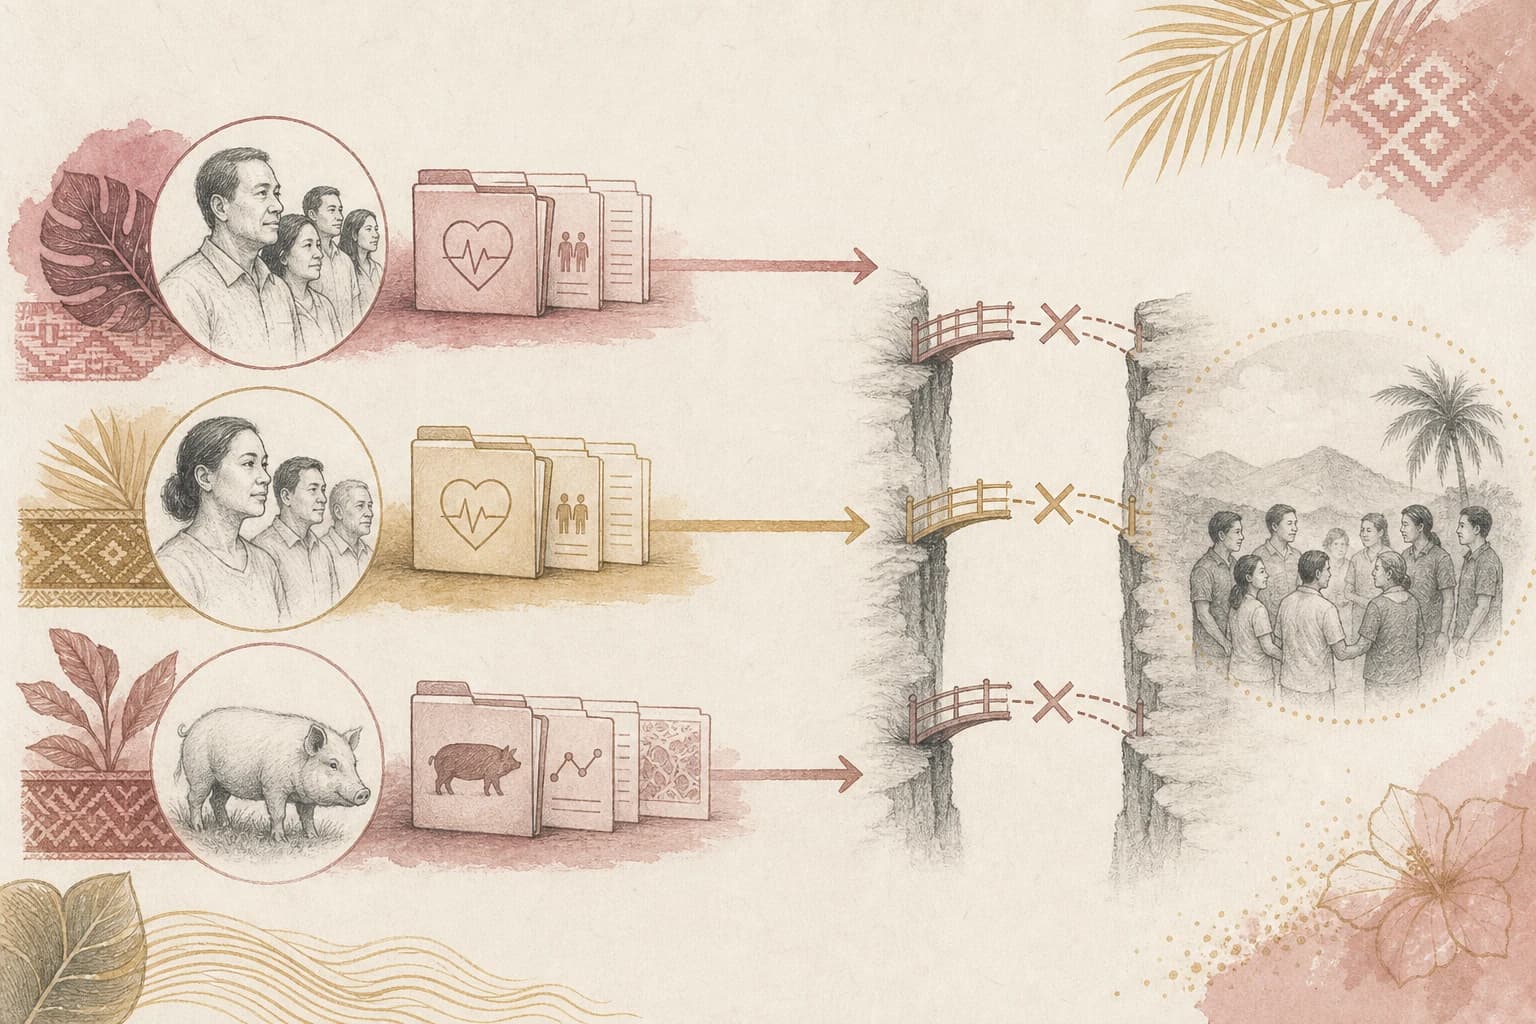
Published studies authenticate their own interventions, not items offered by unrelated sellers. A citation attached to an advertisement cannot bridge that identity gap.
For any semaglutide claim, ask four questions: which form, which named product, which population, and which endpoint? Those details quickly separate a usable study from a borrowed headline.
How should the final comparison be read?
Oral and injectable semaglutide are related evidence tracks, not identical files.
Oral semaglutide has direct cardiovascular outcome evidence in SOUL’s defined population.1 Weekly injectable semaglutide has randomized comparisons with other injectable diabetes treatments.4
Neither record lets readers invent a universal winner. Route preference, access, clinical context, and authorized product details sit outside a simple efficacy headline.
Preclinical delivery work belongs on a separate tier. It may guide later research, but it cannot replace human trials or local regulatory verification.35
The most accurate article keeps every conclusion attached to its exact source, study context, and product identity.6 That discipline is more informative than flattening all semaglutide evidence into one claim.
Bottom line
Oral and injectable semaglutide share an active ingredient, but their evidence should remain attached to the exact form studied. SOUL provides cardiovascular outcome evidence for oral semaglutide in older adults with type 2 diabetes and elevated cardiovascular or kidney risk.
Injectable trials answer different comparison questions, and the minipig film experiment remains preclinical. Filipino readers should verify the exact product and establishment through official local records. The safest comparison names the formulation, study population, endpoint, and source instead of assuming that every semaglutide item carries every published result.
Frequently asked questions
Is oral semaglutide the same molecule as injectable semaglutide?
It uses the same active ingredient, but formulation, route, schedule, and official product records still differ.
Did SOUL study cardiovascular events?
Yes. It assessed a combined endpoint of cardiovascular death, nonfatal heart attack, and nonfatal stroke in a defined high-risk population.1
Did the injectable meta-analysis compare both forms directly?
No. It compared weekly semaglutide with other injectable diabetes treatments, not oral semaglutide.4
Was the thin-film study conducted in people?
No. It involved 40 female Göttingen minipigs and remains preclinical evidence.3
Do the catalog cards prove product equivalence?
No. They are neutral catalog references, while identity and authorization require exact official records.
Sources
Footnotes
-
Oral Semaglutide and CV Benefits in the SOUL Trial: How Do Baseline or Changes in HbA1c or BMI Affect Clinical Outcomes?. SOUL randomized 9,650 adults aged 50 or older with type 2 diabetes and atherosclerotic cardiovascular disease, chronic kidney disease, or both, with median follow-up of 47.5 months. This population-specific outcome does not establish identical cardiovascular evidence for every semaglutide product or form. ↩ ↩2 ↩3 ↩4 ↩5
-
Oral Glucagon-Like Peptide-1 Receptor Agonists for Preventing Cardiorenal Complications.. Review of randomized evidence for oral GLP-1 receptor agonists in people with type 2 diabetes at cardiovascular risk. Non-inferiority and superiority answer different statistical questions and should not be merged. ↩ ↩2
-
Electrospun Nanofiber Oral Thin Film Platform for Sublingual Peptide Delivery: A Promising Alternative to Conventional Semaglutide Formulations.. Preclinical comparison of a sublingual film, oral tablet, under-the-skin form, and placebo. This animal study cannot establish human safety, effectiveness, product equivalence, or Philippine product status. ↩ ↩2 ↩3 ↩4 ↩5
-
Efficacy and Safety of Once-Weekly Semaglutide Versus Basal Insulin and Other GLP-1 Receptor Agonists in Adults With Type 2 Diabetes Uncontrolled on Oral Antidiabetic Drugs: A Systematic Review and Pairwise Meta-Analysis.. Pairwise comparisons with basal insulin or other GLP-1 receptor agonists in adults with type 2 diabetes uncontrolled on oral medicines. Several findings had low certainty because of heterogeneity, open-label designs, and manufacturer sponsorship; the analysis did not compare weekly semaglutide with oral semaglutide. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Official Philippine regulatory verification service. A portal record applies to the exact product or establishment named in that record. ↩ ↩2 ↩3
-
Oral Semaglutide and CV Benefits in the SOUL Trial: How Do Baseline or Changes in HbA1c or BMI Affect Clinical Outcomes?; Oral Glucagon-Like Peptide-1 Receptor Agonists for Preventing Cardiorenal Complications.; Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Editorial synthesis of the canonical research records and Philippine verification sources. This synthesis is educational and is not personal medical advice or a product recommendation. ↩ ↩2 ↩3
-
Oral Glucagon-Like Peptide-1 Receptor Agonists for Preventing Cardiorenal Complications.. Review of SOUL cardiovascular and kidney findings. This endpoint-specific result should not be generalized to every kidney measure or semaglutide form. ↩
-
WHO laboratory analysis of suspected falsified medical products; WHO laboratory testing for health-product regulation. WHO guidance on suspected falsified medical products and regulatory laboratory testing. Appearance alone cannot authenticate a product or establish a research outcome. ↩


