Quick answer
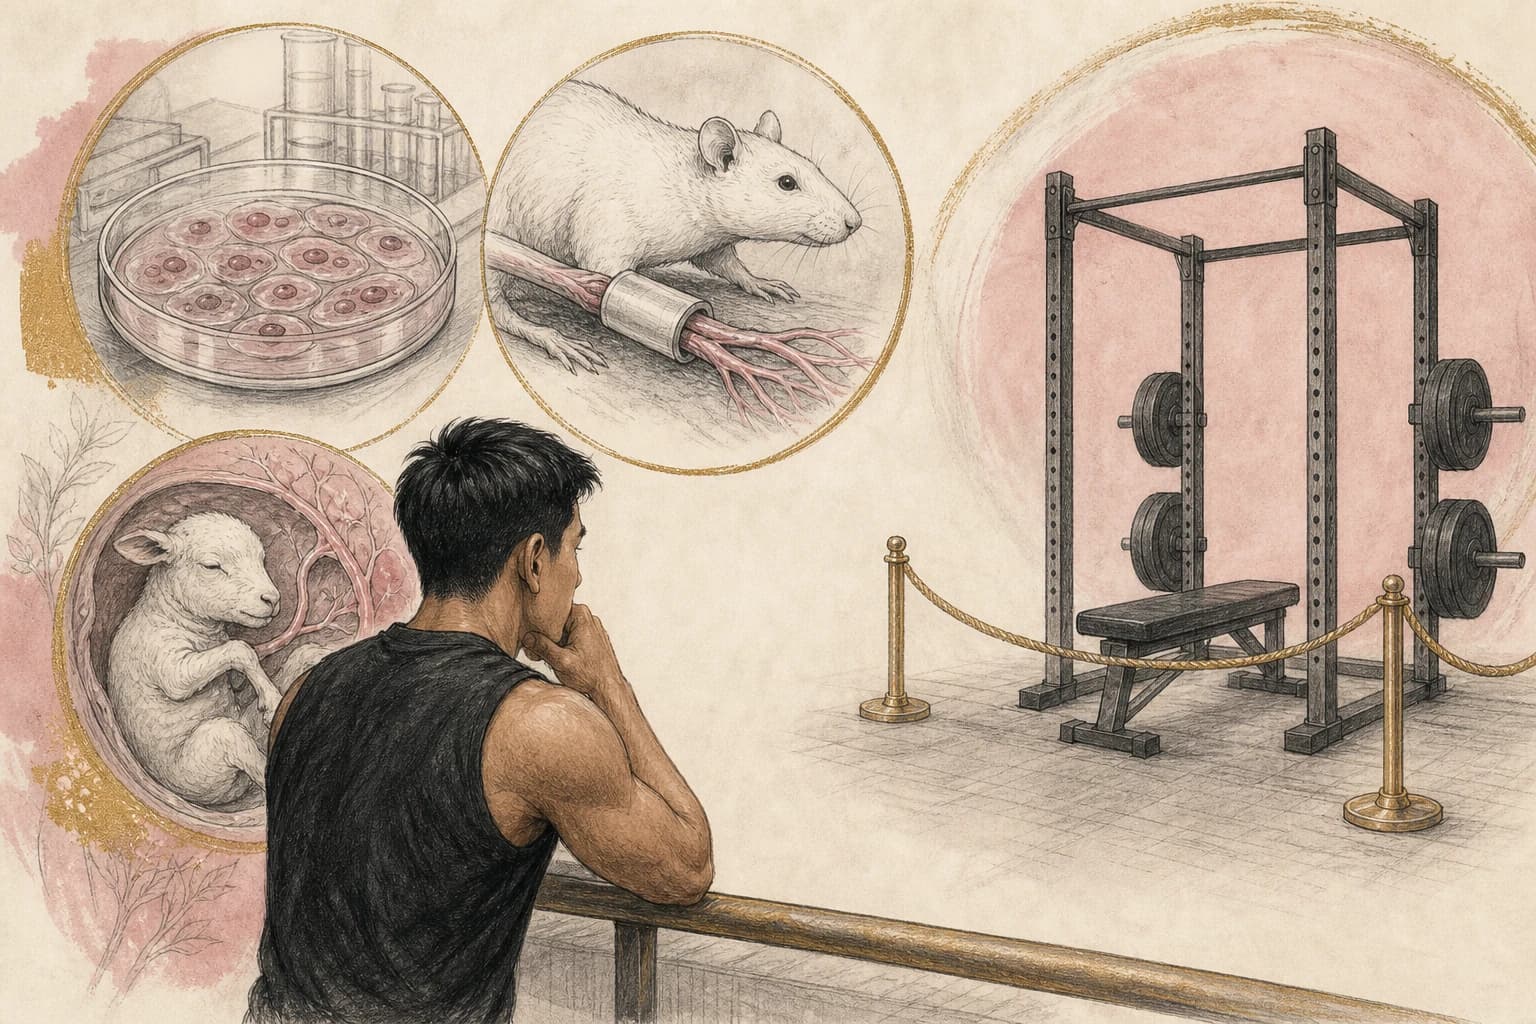
The cited IGF-1 LR3 research does not prove that the compound builds more skeletal muscle in people. The evidence includes receptor signaling in cultured cells, a rat nerve-conduit experiment, and several fetal-sheep studies of growth, insulin, and heart development.
Those are legitimate research contexts, but none is a controlled human trial measuring muscle mass, strength, or training performance. One fetal-sheep study even found no improvement in overall growth. Filipino readers should preserve the species, tissue, and endpoint behind each result instead of translating every growth-related signal into a bodybuilding claim.123
What is IGF-1 LR3 in the laboratory?
IGF-1 LR3 is a synthetic, lengthened analogue of IGF-1. A Chinese hamster ovary cell study used it while examining IGF-1 receptor and ERK signaling under altered glycosylation conditions.1
This type of experiment asks how a signaling pathway behaves in controlled cells. It can show that receptors and downstream signals respond under specific laboratory conditions.
It cannot show that a person gains muscle. Cultured ovary cells are not human skeletal muscle, and receptor activity is several steps removed from whole-body changes in tissue mass or strength.
The word “growth” can make the leap feel natural. Yet biological growth can refer to cells, organs, fetuses, blood vessels, nerves, or tumors. A credible summary names the exact tissue and outcome.
Readers researching IGF-1 LR3 can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
Did the rat nerve study show muscle growth?
No. Researchers built a plant-based biomaterial conduit that released IGF-1 LR3 around an injured rat sciatic nerve. They reported improved experimental regeneration measures.2
The intervention was not simply free IGF-1 LR3. It combined a conduit, gel material, and controlled release within an animal nerve-injury model.
Nerve regeneration may eventually matter to function, but it is not the same endpoint as increasing skeletal-muscle size in healthy people. The study cannot be summarized as a bodybuilding trial.
Delivery also matters. A compound embedded in a local biomaterial may behave differently from another formulation or route. The product in a catalog cannot borrow the conduit’s evidence without matching the complete intervention.
The fair sentence is specific: a controlled-release nerve conduit containing IGF-1 LR3 improved selected regeneration measures in rats. Anything broader requires separate evidence.
What did the fetal-sheep studies find?
The animal results were mixed rather than uniformly growth-promoting.34 In growth-restricted fetal sheep, IGF-1 LR3 did not improve growth compared with vehicle and was associated with lower circulating amino acids.3
An acute fetal-sheep experiment reported lower plasma insulin and lower glucose-stimulated insulin secretion in the living animals. Isolated islets did not differ when collected, creating different in-vivo and laboratory observations.4
A separate one-week study found lower plasma insulin and glucose, lower glucose-stimulated insulin secretion, and lower secretion in isolated fetal islets.5
These are endocrine and developmental findings in late gestation. They do not test adult human muscle gain, and they show why a general “anabolic” label can conceal complex metabolic effects.
Fetal physiology is also unique. Nutrient transfer, organ development, and maternal–fetal relationships make the model unsuitable as a direct picture of a gym user.
Does cardiac growth support a muscle-building claim?
A near-term fetal-sheep experiment reported cardiac growth alongside coronary vascular growth. Coronary conductance per gram was preserved.6
The heart is muscle, but cardiac development is not interchangeable with skeletal-muscle hypertrophy. The outcome involved fetal heart and blood-vessel measurements, not biceps size, lifting performance, or adult exercise adaptation.
Calling every muscle tissue the same erases anatomy and purpose. Cardiac muscle contracts continuously and has a different structure and regulation from skeletal muscle.
The vascular finding also matters. The paper examined whether coronary growth matched cardiac growth, not whether the animals became stronger or more athletic.
Readers comparing this topic with CJC-1295 with DAC can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
Where is the human muscle trial?
It is not present in this evidence bundle. A 2026 review lists IGF-1 LR3 among analogues discussed in performance-peptide markets and contrasts published evidence with online self-delivery.7
The review provides market and clinical context, not a controlled human muscle outcome for IGF-1 LR3. A reader should not confuse inclusion in a review with proof of efficacy.
A useful human trial would define participants, authenticate the intervention, compare it with placebo or another control, and measure muscle using validated methods. Strength, function, adverse events, and follow-up would add meaning beyond a scan.
Muscle mass and muscle performance should both appear. An imaging estimate can change without a matching improvement in force, mobility, or daily activity, while strength can improve through technique and nervous-system adaptation before tissue size changes.
The trial would also need enough participants and time to distinguish a repeatable effect from normal fluctuation. Diet, training experience, age, illness, and concurrent substances can influence the same endpoints.
Safety cannot be an afterthought. Researchers would need to monitor glucose regulation, organ effects, laboratory changes, and adverse events rather than assuming that a growth-related mechanism affects only the intended tissue.
Replication would matter as much as the first result. A finding that appears in one small group should be tested independently before it becomes a confident claim for a broad market.
Transparent reporting would also reveal neutral outcomes and participant withdrawals.
Until such evidence appears, cell signaling and animal development remain preclinical. They can justify scientific questions, but not a confident human result.
How can Filipino readers audit a “more muscle” post?
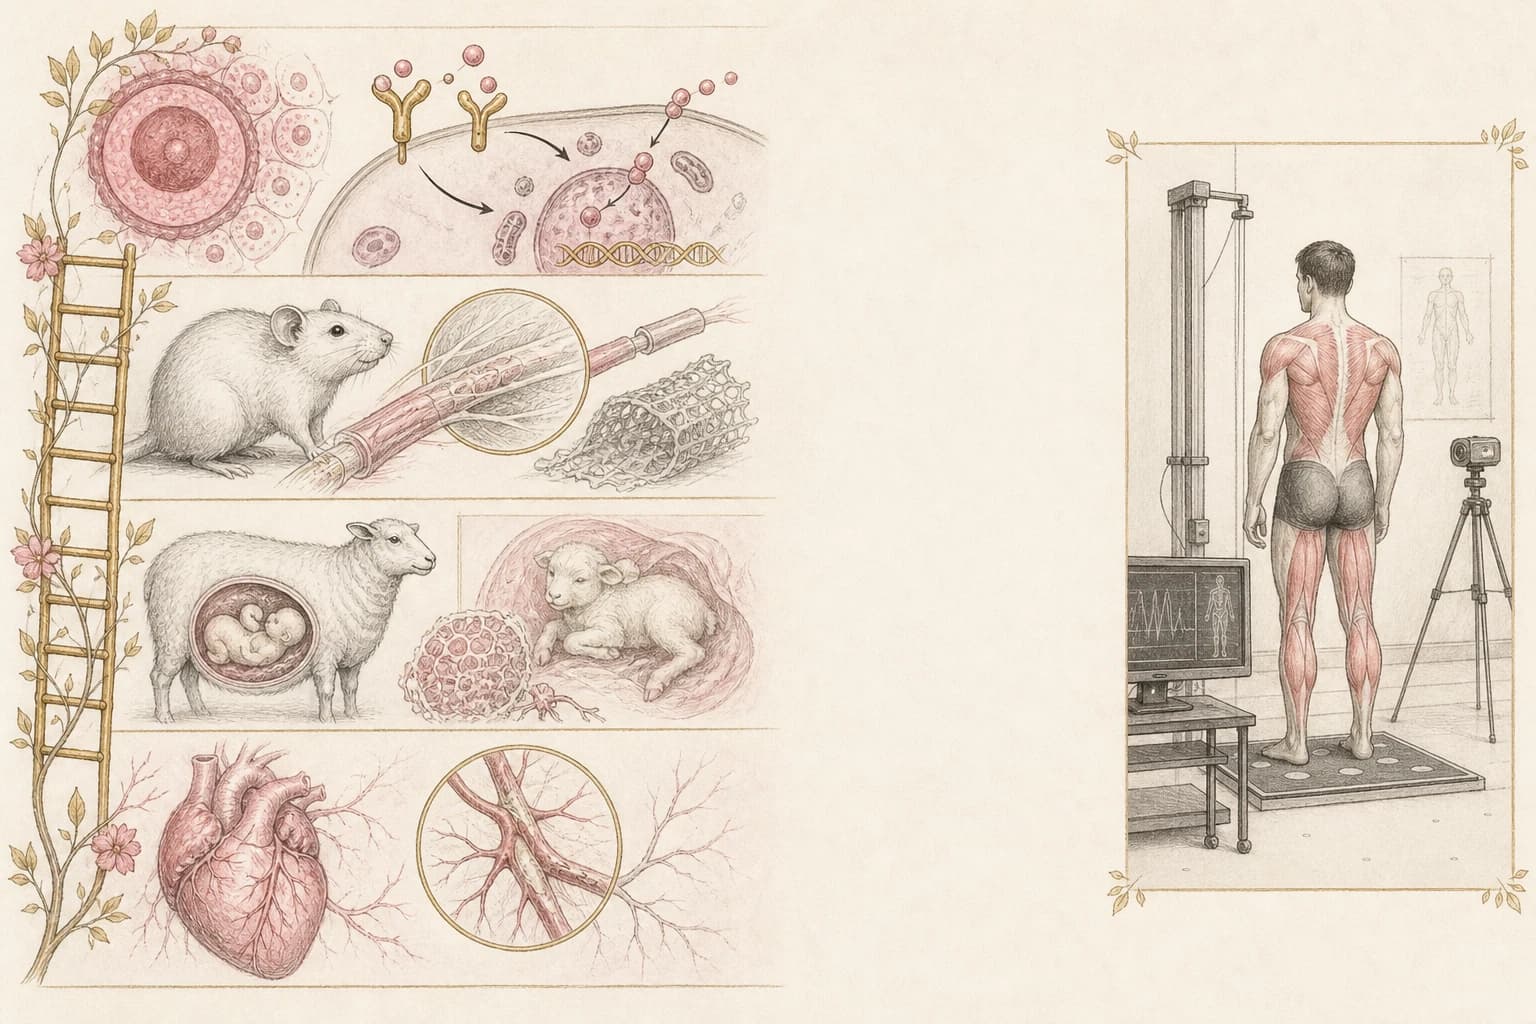
Find the noun after “growth.” Was it receptor signaling, a regenerating nerve, fetal body mass, the heart, blood vessels, or human skeletal muscle?
Check the species and life stage. Cells, rats, and fetal sheep do not represent adult Filipino gym users.123
Identify the complete intervention. A controlled-release biomaterial cannot verify a separate product or route.2
Look for both favorable and unfavorable findings.34 The no-growth fetal-sheep result and differing insulin observations should appear beside any positive experimental result.34
Finally, ask whether muscle mass or performance was measured directly. If not, the article should describe biology, not promise bodybuilding outcomes.
Bottom line
IGF-1 LR3 has interesting laboratory and animal research, but this research reviewed here does not contain a controlled human trial proving more skeletal muscle. Cell signaling, rat nerve regeneration, fetal-sheep metabolism, and fetal cardiac growth are different endpoints in different models.
The evidence is also mixed: one fetal-sheep study found no improvement in overall growth, while insulin findings varied across experiments. Filipino readers should ask which tissue grew, in which species, under what intervention, and whether human muscle or performance was measured. Laboratory biology can inspire a clinical question; it cannot answer that question by itself.
Frequently asked questions
Is IGF-1 LR3 a modified IGF-1 analogue?
Yes. Cell research describes it as a synthetic, lengthened analogue.1
Did the rat study measure human muscle growth?
No. It studied a controlled-release nerve conduit in rats.2
Did IGF-1 LR3 improve fetal-sheep growth?
One study found no improvement compared with vehicle.3
Does fetal heart growth prove adult skeletal-muscle gain?
No. The tissue, species, life stage, and outcome are different.6
Do the cards recommend combining IGF-1 LR3 with CJC-1295?
No. They are separate catalog references and do not recommend combinations, amount guidance, treatment, or human use.
Sources
Footnotes
-
N-Linked Glycosylation in Chinese Hamster Ovary Cells Is Critical for Insulin-like Growth Factor 1 Signaling. Chinese hamster ovary cell experiment. Cell signaling is a laboratory endpoint, not a clinical muscle outcome. ↩ ↩2 ↩3 ↩4
-
Revolutionary decellularized Alstroemeria stem-based nerve conduit integrated with GelMA and controlled IGF-1 LR3 release for enhanced rat sciatic nerve regeneration. Rat sciatic-nerve conduit experiment. The result concerns a controlled-release biomaterial in rats, not muscle change in people. ↩ ↩2 ↩3 ↩4 ↩5
-
IGF-1 LR3 does not promote growth in late-gestation growth-restricted fetal sheep. Late-gestation fetal-sheep growth-restriction model. This is a negative animal growth result, not a human body-composition outcome. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7
-
Attenuated glucose-stimulated insulin secretion during an acute IGF-1 LR3 infusion into fetal sheep does not persist in isolated islets. Acute fetal-sheep experiment with in vivo and isolated-islet measurements. The in vivo and isolated-islet observations differ and are not clinical outcomes. ↩ ↩2 ↩3 ↩4
-
Reduced glucose-stimulated insulin secretion following a 1-wk IGF-1 infusion in late gestation fetal sheep is due to an intrinsic islet defect. One-week late-gestation fetal-sheep experiment. This is an animal endocrine experiment, not a study of human muscle outcomes. ↩
-
Coronary vascular growth matches IGF-1-stimulated cardiac growth in fetal sheep. Near-term fetal-sheep cardiovascular experiment. Cardiac and coronary measurements in fetal sheep are separate from skeletal-muscle outcomes in people. ↩ ↩2
-
The emerging landscape of performance-enhancing peptides modulating GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration. Narrative review of peptides connected with the GH-IGF-1 axis. The review provides broad market and clinical-context framing; it is not a human muscle trial of IGF-1 LR3. ↩