TL;DR
- GLP-1 agonists and amylin analogues belong to different research lanes because they engage different receptors, even when scientists study them together.1
- Semaglutide has randomized human evidence from STEP 1, where its group result was measured against placebo and lifestyle support over 68 weeks.2
- Cagrilintide-semaglutide was tested in REDEFINE 1, but its group average remains specific to that population, protocol, comparator, and follow-up.3
- 5-amino-1MQ sits much earlier on the research map: published findings discussed here come from cells and diet-induced obese mice, not comparable human trials.4
For Filipino readers, names such as GLP-1, amylin, “dual agonist,” and “metabolic compound” can blur into one busy headline. The science is easier to read when each label is placed on a map. Some compounds copy hormone signals.5 Others reach several receptors.6 Still others begin with an enzyme in cells or a mouse experiment.4 Those categories tell us what question was tested, not which name should win.7
Build the map before the scoreboard
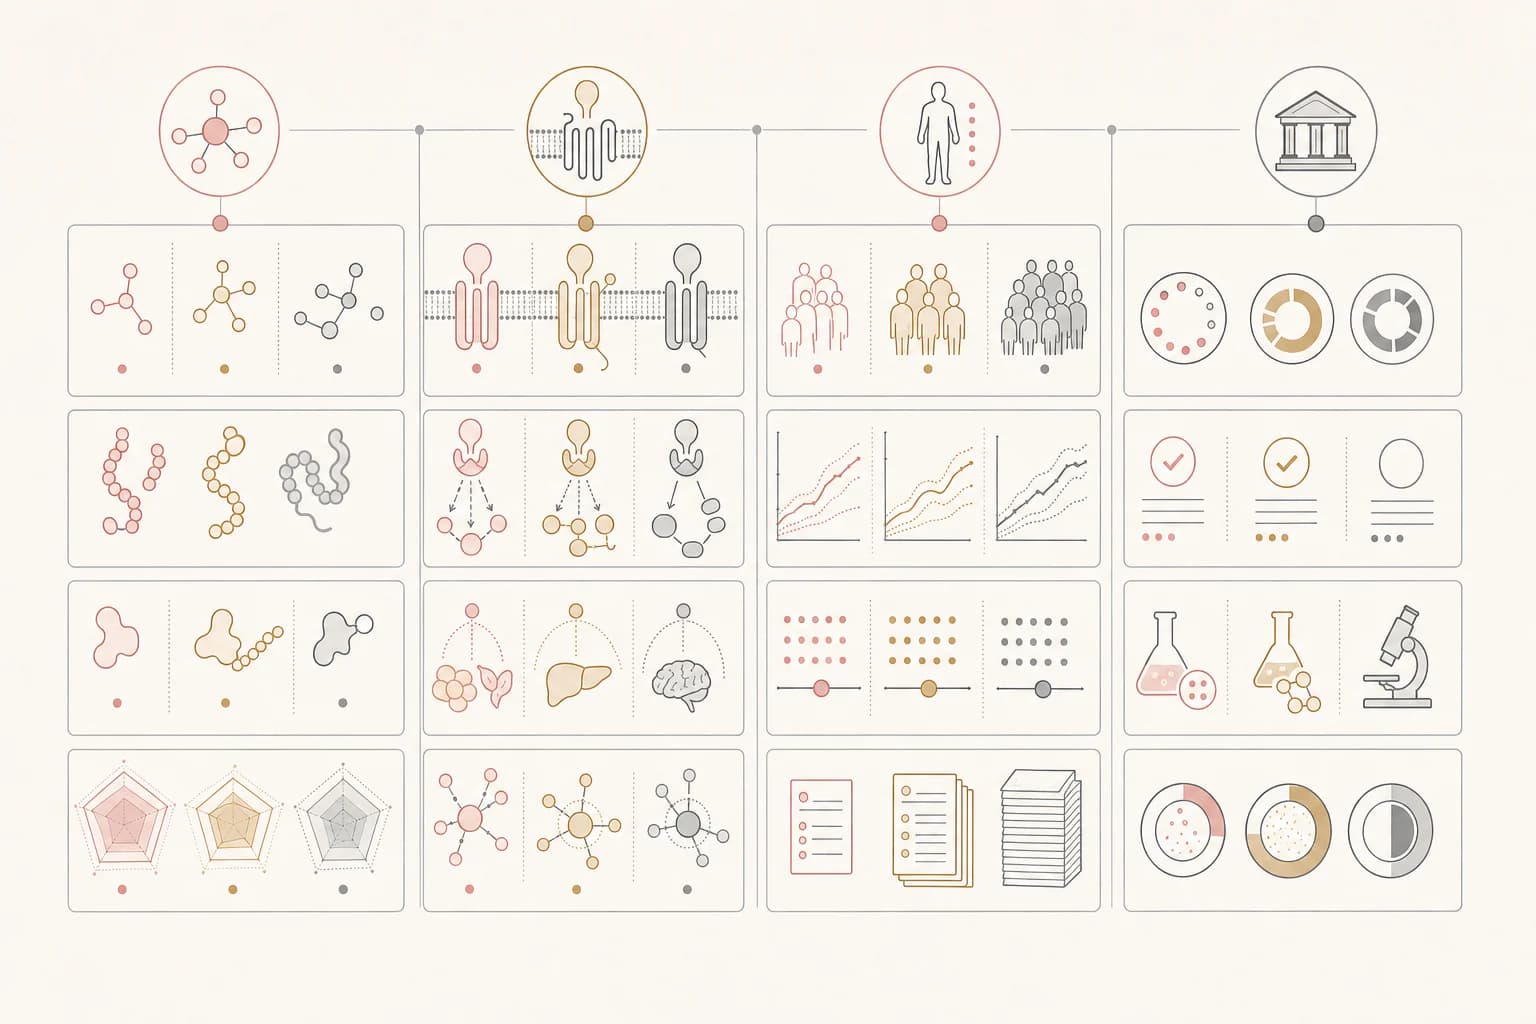
A GLP-1 agonist activates the GLP-1 receptor, while an amylin analogue is designed around another hormone pathway.5 These labels describe biological targets, not a shared level of evidence.7 Semaglutide represents the single GLP-1 lane in this comparison.8 Cagrilintide belongs to long-acting amylin research and has amylin and calcitonin receptor activity.1
Multi-receptor compounds create another lane by engaging two or three named receptors within one design.6 Small molecules aimed at an enzyme, such as 5-amino-1MQ, form a different category again.4 A human randomized trial, a review, a cell assay, and a mouse study answer different questions.7 The useful comparison therefore begins with target, model, study phase, population, comparator, and follow-up.7
Semaglutide is named here only as the neutral catalog reference below.
The GLP-1 lane has a human benchmark
GLP-1 and GIP are incretins that bind their own receptors and influence food-intake signaling.5 Both also stimulate insulin release from pancreatic beta cells, though their effects on glucagon signaling differ with metabolic conditions.5 Semaglutide acts through the GLP-1 receptor rather than the amylin, GIP, or glucagon receptors.8
STEP 1 offers a clear human example.8 The double-blind trial enrolled 1,961 adults with obesity, or overweight plus a related condition, who did not have diabetes.8 Researchers compared semaglutide with placebo for 68 weeks, with lifestyle support in both groups.8 Mean body-weight change was -14.9% in the semaglutide group and -2.4% with placebo.2 Nausea and diarrhea were the most common adverse events in the report.2
Those numbers describe groups under one protocol.2 They are a benchmark for that trial, not a forecast for an individual or a universal score for every metabolic compound.7
Amylin follows a different route
Amylin research starts from a pancreatic hormone pathway, not from the GLP-1 receptor.1 A recent review describes long-acting amylin-related compounds as a distinct design family.1 Cagrilintide has activity at amylin and calcitonin receptors, which separates its target map from semaglutide.1
That separation explains why scientists study the two pathways together.1 The idea is complementary signaling: one compound reaches GLP-1 biology while the other reaches amylin-related biology.1 A plausible pairing remains a research question until a direct trial tests outcomes and adverse events.9
The distinction also keeps language honest.7 “Analogue,” “single agonist,” and “combination” are not synonyms.1 They identify different biological designs and study questions.7 Mechanism can explain why a comparison was planned, but the measured result comes from the enrolled population and chosen comparator.9
A combination must earn its own result
REDEFINE 1 tested cagrilintide and semaglutide together rather than assuming their effects would add up.9 The 68-week phase 3 trial randomized 3,417 adults without diabetes.9 Participants had obesity, or overweight with at least one related complication.9 Trial groups included the combination, each component alone, and placebo, while all groups received lifestyle support.9
The published primary comparison found an estimated mean change of -20.4% with the combination and -3.0% with placebo.3 That finding belongs to the trial’s group analysis and cannot become a claim about a catalog item.3 Safety belongs beside the outcome.10 Gastrointestinal adverse events appeared in 79.6% of the combination group and 39.9% of the placebo group.10 The report described them as mainly short-lived and mild to moderate.10 A 68-week record also cannot settle uncommon or longer-term outcomes.10
Cagrilintide is named here only as the neutral catalog reference below.
Dual and triple designs widen the target map
Tirzepatide represents a dual-receptor strategy because it engages GIP and GLP-1 receptors.6 SURMOUNT-1 compared it with placebo in 2,539 adults without diabetes over 72 weeks.6 That phase 3 record belongs to its own design and population.6
Retatrutide widens the map again by engaging GIP, GLP-1, and glucagon receptors.11 Its published phase 2 trial enrolled 338 adults and followed them for 48 weeks.11 The trial reported body-weight changes that varied across retatrutide groups and differed from placebo.11 Gastrointestinal events were the most common, while heart-rate increases rose with study group strength, peaked at week 24, and later declined.12
More receptors do not automatically mean stronger evidence.7 A phase 2 triple-receptor trial and a phase 3 dual-receptor trial sit at different points in development.6 Their percentages cannot serve as a clean head-to-head ranking.7
Small molecules may begin far from hormone receptors
The phrase “metabolic research compound” can cover work that is neither incretin nor amylin science.4 5-amino-1MQ is one example.4 It is a small molecule studied as an inhibitor of nicotinamide N-methyltransferase, usually shortened to NNMT.4 Researchers examined related inhibitors in cultured fat cells and diet-induced obese mice.4
A later 28-day mouse study measured body composition, glucose, insulin, liver tissue, blood markers, and how 5A1MQ moved through tissues.13 The authors reported less body-weight and fat-mass gain, along with changes in glucose, insulin, and liver measures.13 These are animal findings from a defined laboratory model.13 They do not establish matching human outcomes and cannot be placed beside human trial percentages as though the measurements were equivalent.13
The lesson is not to dismiss early research.4 It is to name the model before describing the finding.13
Read comparisons in six passes
First, identify the target: GLP-1, amylin-related receptors, several hormone receptors, or an enzyme such as NNMT.5 Second, check whether the design uses one compound, a co-studied pair, or a multi-receptor molecule.1 Third, name the model: cells, mice, or enrolled adults.4
Fourth, find the comparator, because placebo and active-comparator questions are not interchangeable.9 Fifth, note study phase and follow-up; the trials here span phase 2 and phase 3 designs with different timelines.7 Sixth, read adverse events beside the main outcome.2
This method blocks the most tempting shortcut.7 A larger percentage printed in one paper does not prove that its compound outperformed a name from another paper.7 Only a suitable direct comparison can answer that narrower question.7 Until then, the careful unit of reading is the whole study, not its biggest number.7
Bottom line
GLP-1 agonists, amylin analogues, multi-receptor compounds, and enzyme-focused small molecules are not one research category.7 Semaglutide supplies a single-receptor human trial example, while cagrilintide adds a distinct amylin-related pathway in combination research.8 Tirzepatide and retatrutide show how dual and triple designs broaden receptor targets.6 5-amino-1MQ shows a much earlier cell-and-mouse route centered on NNMT.4 The sound comparison asks what was tested, in whom or what model, against which control, and for how long.7
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Frequently asked questions
Are GLP-1 agonists and amylin analogues the same?
No. GLP-1 agonists act at the GLP-1 receptor, while amylin analogues are built around amylin-related signaling.1 They may be studied together because their targets differ.1 That biological rationale does not make their evidence or measured effects interchangeable.7 A direct study must test any measured difference.9
Where does semaglutide fit in this comparison?
Semaglutide is the single GLP-1 receptor example here.8 STEP 1 compared it with placebo plus lifestyle support in adults without diabetes for 68 weeks.8 Its reported mean belongs to that trial population and should not be used as a universal forecast.2 The comparator and enrolled group are essential context.8
Why is cagrilintide discussed beside semaglutide?
Cagrilintide has amylin and calcitonin receptor activity, while semaglutide acts at the GLP-1 receptor.1 REDEFINE 1 studied the pair in a randomized human trial with component and placebo groups.9 The catalog cards remain neutral references, not research evidence.3 The result stays tied to its participants and protocol.3
What makes a compound dual or triple?
The label counts named receptor systems engaged by one design.6 Tirzepatide engages GIP and GLP-1 receptors, making it dual.6 Retatrutide engages GIP, GLP-1, and glucagon receptors, making it triple.11 The count alone does not rank evidence strength.7 Study phase and comparator still shape interpretation.7
Can percentages from separate trials be ranked?
Not as a clean head-to-head result.7 STEP 1, SURMOUNT-1, REDEFINE 1, and the retatrutide study differed in compounds, groups, phases, timelines, and analysis plans.7 Each percentage must stay attached to its own comparator and study context.7 Direct comparisons require a suitable shared design.7
What does the 5-amino-1MQ research show?
Published work discussed here places 5-amino-1MQ in NNMT-focused cell and mouse research.4 A 28-day mouse study reported changes in body composition and several metabolic measures.13 Those animal findings do not establish matching results in people.13 A human trial would answer a different question.13
Sources
Footnotes
-
Long-acting amylin-related peptides as therapies for obesity and type 2 diabetes.. Narrative review of long-acting amylin-related peptides. Mechanistic difference provides a research rationale, not proof of a superior clinical result. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12
-
Once-Weekly Semaglutide in Adults with Overweight or Obesity.. Both groups received lifestyle intervention, and adults with diabetes were excluded. A group mean does not describe every participant, and this was not a comparison with amylin or multi-receptor compounds. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity.. Adults had obesity or overweight with at least one related complication and did not have diabetes. The figures are group estimates under that protocol and should not be converted into a catalog-product promise. ↩ ↩2 ↩3 ↩4 ↩5
-
Selective and membrane-permeable small molecule inhibitors of nicotinamide N-methyltransferase reverse high fat diet-induced obesity in mice.; Nicotinamide N-methyltransferase inhibition mitigates obesity-related metabolic dysfunction.. Laboratory assays and two animal pharmacology studies. The research models and target differ from the human incretin and amylin trials. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
Mechanisms of action and therapeutic applications of GLP-1 and dual GIP/GLP-1 receptor agonists.. Mechanistic review covering GLP-1 and dual GIP/GLP-1 receptor agonists. A mechanism review does not establish a clinical outcome for every compound that reaches these receptors. ↩ ↩2 ↩3 ↩4 ↩5
-
Tirzepatide Once Weekly for the Treatment of Obesity.. Phase 3, double-blind, randomized human trial with multiple tirzepatide groups. The study used its own doses, population, duration, and estimand, so its percentages are not a direct ranking against other trials. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity.; Triple-Hormone-Receptor Agonist Retatrutide for Obesity - A Phase 2 Trial.; Once-Weekly Semaglutide in Adults with Overweight or Obesity.; Tirzepatide Once Weekly for the Treatment of Obesity.. Comparison of four separate randomized trial records. Each result should be read with its own comparator, phase, population, endpoint, and follow-up. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15 ↩16 ↩17 ↩18 ↩19 ↩20 ↩21 ↩22 ↩23
-
Once-Weekly Semaglutide in Adults with Overweight or Obesity.. Randomized, double-blind human trial in adults with obesity or overweight plus a related condition. The result belongs to the trial population, comparator, follow-up, and analysis. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity.. Phase 3a, multicenter, double-blind, placebo-controlled and active-controlled human trial. The primary published comparison was cagrilintide-semaglutide versus placebo. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Coadministered Cagrilintide and Semaglutide in Adults with Overweight or Obesity.. Safety reporting from the 68-week REDEFINE 1 trial. One trial duration cannot settle uncommon or longer-term outcomes. ↩ ↩2 ↩3 ↩4
-
Triple-Hormone-Receptor Agonist Retatrutide for Obesity - A Phase 2 Trial.. Randomized, double-blind, placebo-controlled phase 2 human trial. A phase 2 result under one protocol is not interchangeable with phase 3 evidence for another compound. ↩ ↩2 ↩3 ↩4
-
Triple-Hormone-Receptor Agonist Retatrutide for Obesity - A Phase 2 Trial.. Safety observations over 48 weeks in adults enrolled in the phase 2 trial. The study authors stated that dose-response relationships for safety and efficacy were not known before this trial, and further phases answer different questions. ↩
-
Nicotinamide N-methyltransferase inhibition mitigates obesity-related metabolic dysfunction.. Animal pharmacology study with body-composition, laboratory, histology, and pharmacokinetic measurements. Mouse findings do not establish the same outcomes in people and cannot be compared numerically with human randomized trials. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8