Quick answer
Tesamorelin has real human trial evidence, but it is much narrower than common wellness and physique marketing suggests. A meta-analysis found lower visceral adipose tissue in adults with HIV-associated lipodystrophy. It did not find significant reductions in body mass index or subcutaneous fat.
That result does not prove generic weight loss, muscle gain, faster recovery, or equivalence with every growth-hormone-pathway peptide. Filipino readers should keep the population, fat compartment, endpoint, product identity, and local regulatory record visible before trusting a promotional claim.12345
Claim 1: “Tesamorelin is a general weight-loss peptide”
The human evidence does not support that broad wording.
A meta-analysis combined five randomized controlled trials in adults with HIV-associated lipodystrophy.1
It found a significant reduction in visceral adipose tissue with tesamorelin compared with placebo.1
The same analysis found no significant reduction in body mass index.1 BMI is not a perfect measure, but its result matters when someone markets the intervention as general weight loss.
The study population was also specific. Adults with HIV-associated lipodystrophy have a defined clinical context that cannot be replaced with “anyone who wants to lose weight.”
A more accurate summary is that tesamorelin reduced a particular fat compartment in a particular population under trial conditions.
That may be clinically meaningful without becoming a universal slimming claim.
Readers researching Tesamorelin can view its live catalog details below. The listing identifies the catalog item and is separate from the evidence discussed here.
Claim 2: “It removes every kind of belly fat”
Visceral and subcutaneous fat are different compartments.
Visceral fat sits deeper in the abdomen around internal organs. Subcutaneous fat lies beneath the skin.
The tesamorelin meta-analysis reported lower visceral adipose tissue but no significant reduction in subcutaneous adipose tissue.1
That contrast is exactly why “belly fat” is too vague for evidence-based writing. The phrase can refer to several tissues, body measurements, or appearance changes.
A photograph cannot identify which compartment changed. Even waist circumference does not perfectly separate visceral from subcutaneous tissue.
Clinical studies may use imaging to measure compartments more directly. Their results should be reported using the same anatomical term.
Marketing that turns a visceral-fat result into “melts all abdominal fat” discards the study’s most important boundary.
Claim 3: “A higher GH or IGF-1 signal proves muscle gain”
Hormone markers show biological activity, not automatic changes in muscle, strength, or performance.
Tesamorelin, sermorelin, and CJC-1295 are classified as growth hormone-releasing hormone analogues. Ipamorelin belongs to a related but different secretagogue category.2
In two short randomized trials, CJC-1295 produced sustained increases in growth hormone and IGF-I markers in healthy adults.3
Those trials focused on pharmacokinetics, hormone signals, and short-term safety. They did not directly establish muscle gain or athletic performance.3
This example helps audit tesamorelin marketing because the reasoning error is the same. A pathway change cannot be renamed as a practical outcome that was never measured.
Trials need direct body-composition, strength, function, or recovery endpoints before making those claims.
A higher number may confirm target engagement while still leaving the reader’s real question unanswered.
Claim 4: “All GH-pathway peptides work the same”
Shared pathway language does not make molecules or evidence interchangeable.
Tesamorelin, sermorelin, and CJC-1295 sit in one analogue category, while ipamorelin is classified as a growth hormone secretagogue.2
Each compound has its own structure, exposure pattern, trial population, and endpoint history.
An ipamorelin phase 2 trial after bowel resection found no significant difference from placebo in key or secondary efficacy analyses.4
That negative result belongs to the postoperative bowel setting. It neither disproves every possible question nor supplies evidence for tesamorelin.
The lesson is identity discipline. A positive result for one molecule cannot rescue an unsupported claim for another, and a negative result cannot be copied indiscriminately either.
Readers should ask whether the citation names the exact compound used in the headline.
Readers comparing this topic with Sermorelin can view its live catalog details below. It is a separate catalog reference, not a suggested combination.
Claim 5: “A foreign approval proves every tesamorelin item is approved”
An official approval belongs to the exact named product, applicant, formulation, jurisdiction, and indication.
The United States FDA record lists a tesamorelin product under a specific application.6 That record does not authenticate every catalog item using the ingredient name.
It also does not automatically establish Philippine authorization. Local records must be checked separately.
Marketing often shortens “a named medicine is approved for a defined use” into “tesamorelin is approved.” That wording hides the boundaries readers need.
Regulatory status is not a quality that floats from one product to another. It follows the record.
A seller’s claim should therefore identify the agency and exact product. If those details are missing, the word “approved” cannot be properly audited.
What does the evidence support?
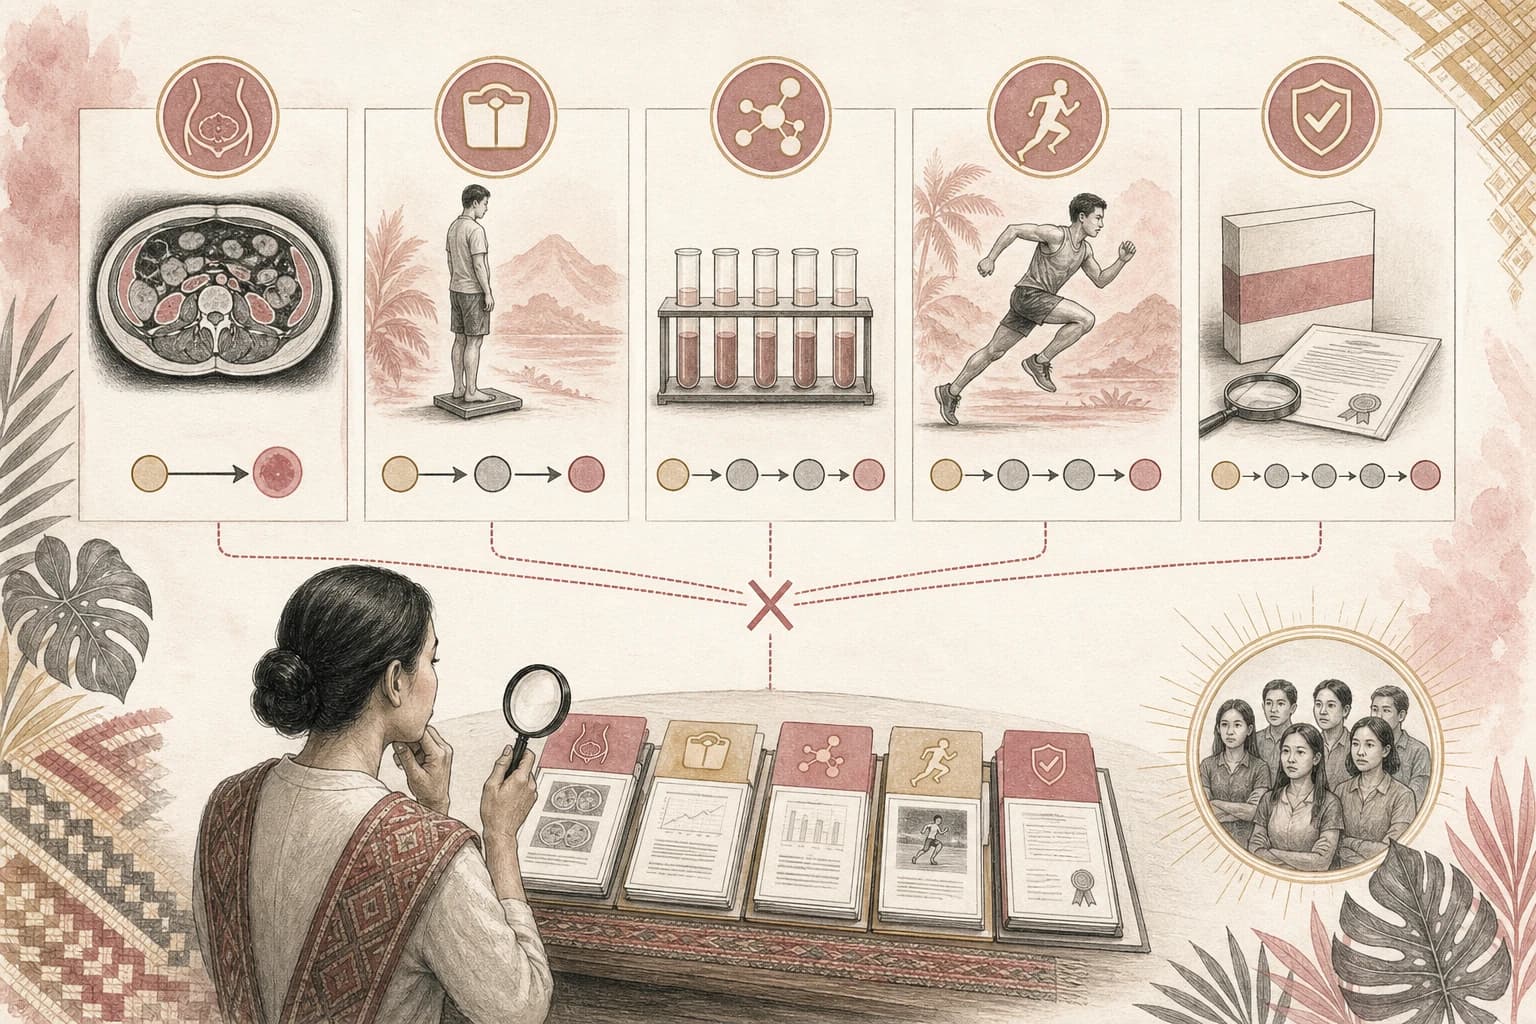
The strongest source in this review supports a narrow, positive claim about visceral adipose tissue in adults with HIV-associated lipodystrophy.1
It does not support significant BMI or subcutaneous-fat reduction in that meta-analysis.1
Related pathway research shows why hormone markers, body-composition outcomes, and performance claims must remain separate.23
The ipamorelin trial adds another useful reminder: a compound can change biological signals without producing the hoped-for efficacy result in a particular setting.4
This evidence is not “anti-peptide.” It is pro-specificity. It preserves what the trials actually found and prevents marketing from stretching one result across five different promises.
Readers can still find the visceral-fat result interesting while refusing unsupported claims about total weight, muscle, recovery, or universal wellness.
What should Filipino readers verify?
The Philippine FDA Verification Portal separates licensed establishments from registered or notified health products.5
Search the exact product and company name, then compare the listed form and current status. Check the establishment record separately.
A licensed business does not prove that every product it offers has a matching authorization.
WHO notes that some falsified medical products can closely resemble genuine ones and may require quality-control analysis.7
Packaging, seals, and online reviews therefore cannot confirm identity. A published tesamorelin study only supports the controlled intervention used in that study.
For any advertisement, write down the claim in one sentence. Then identify the exact molecule, population, endpoint, comparator, duration, and official product record.
If the citation does not support those details, the marketing claim remains unverified.
Bottom line
Tesamorelin’s human evidence is real but specific. Five randomized trials support a reduction in visceral adipose tissue among adults with HIV-associated lipodystrophy, while the same meta-analysis found no significant BMI or subcutaneous-fat reduction.
That record does not prove generic weight loss, muscle gain, faster recovery, or equivalence with every GH-pathway peptide. A foreign product approval also cannot authenticate a Philippine catalog item. Readers should keep the exact compound, study population, fat compartment, measured outcome, and local regulatory record attached to every claim.
Frequently asked questions
Did tesamorelin reduce visceral fat in human trials?
Yes. The cited meta-analysis reported a significant reduction versus placebo in adults with HIV-associated lipodystrophy.1
Did the same analysis show lower BMI?
No. It found no significant BMI reduction.1
Is visceral fat the same as subcutaneous fat?
No. They are different anatomical compartments, and the cited analysis reported different results for them.
Are tesamorelin and sermorelin interchangeable?
No. They are different molecules with separate product and evidence records.
Do the catalog cards recommend using either product?
No. They are neutral catalog references and provide no medical or amount guidance advice.
Sources
Footnotes
-
Body composition, hepatic fat, metabolic, and safety outcomes of Tesamorelin, a GHRH analogue, in HIV-associated lipodystrophy: A meta-analysis of randomized controlled trials. Human randomized-trial meta-analysis in adults with HIV-associated lipodystrophy. The defined population and outcomes do not support a general weight-loss claim. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
The emerging landscape of performance-enhancing peptides modulating GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration.. Narrative review of compounds that affect the GH-IGF-1 axis. A shared pathway category does not make evidence, uses, or outcomes interchangeable. ↩ ↩2 ↩3 ↩4
-
Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults.. Short human trials in healthy adults. Hormone markers are not direct evidence of muscle gain, fat loss, recovery, or performance. ↩ ↩2 ↩3 ↩4
-
Prospective, randomized, controlled, proof-of-concept study of the Ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients.. Human postoperative bowel study. This setting does not answer bodybuilding or general wellness questions. ↩ ↩2 ↩3
-
Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Official Philippine regulatory verification service. A portal record applies to the exact product or establishment named in that record. ↩ ↩2
-
Body composition, hepatic fat, metabolic, and safety outcomes of Tesamorelin, a GHRH analogue, in HIV-associated lipodystrophy: A meta-analysis of randomized controlled trials; The emerging landscape of performance-enhancing peptides modulating GH-IGF1 axis: bridging the gap between clinical evidence and patient self-administration.; Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults.; Philippine FDA Verification Portal; FDA Advisory No. 2023-2238: Utilization of the FDA Verification Portal. Editorial synthesis of the canonical research records and Philippine verification sources. This synthesis is educational and is not personal medical advice or a product recommendation. ↩
-
WHO laboratory analysis of suspected falsified medical products; WHO laboratory testing for health-product regulation. WHO guidance on suspected falsified medical products and regulatory laboratory testing. Appearance alone cannot authenticate a product or establish a research outcome. ↩