
TL;DR
- A biomarker is a measured sign of biology, but movement in that number does not automatically establish a meaningful health outcome for the person tested.1
- Broad panels can manufacture drama: under a simplified central-95-percent model, 20 independent tests give a 64.2 percent chance that one result lands outside range.2
- Useful screening connects a suitable test to a defined population, informed interpretation, quality control, and a workable follow-up path rather than ending at a colorful dashboard.3
- A randomized NAD+ precursor study changed muscle markers of NAD+ synthesis without changing several major metabolic, cardiovascular, and inflammatory measures over six weeks.4
For Filipino readers, the appeal of one blood draw and a grand tour of the body is easy to understand. A polished report can seem like a health map, especially when every organ gets a score. Yet the central question is smaller: what decision will each number improve? The answer depends on the marker, the person, the laboratory, and the next step.3
Start with the job of each number
A biomarker is a measured characteristic that indicates normal biology, a disease process, or a biological response.5 Blood pressure, a blood chemical, or a feature on an image can play that role when used in a defined setting.5 The word itself does not tell us whether the marker can screen, diagnose, predict, or monitor.5
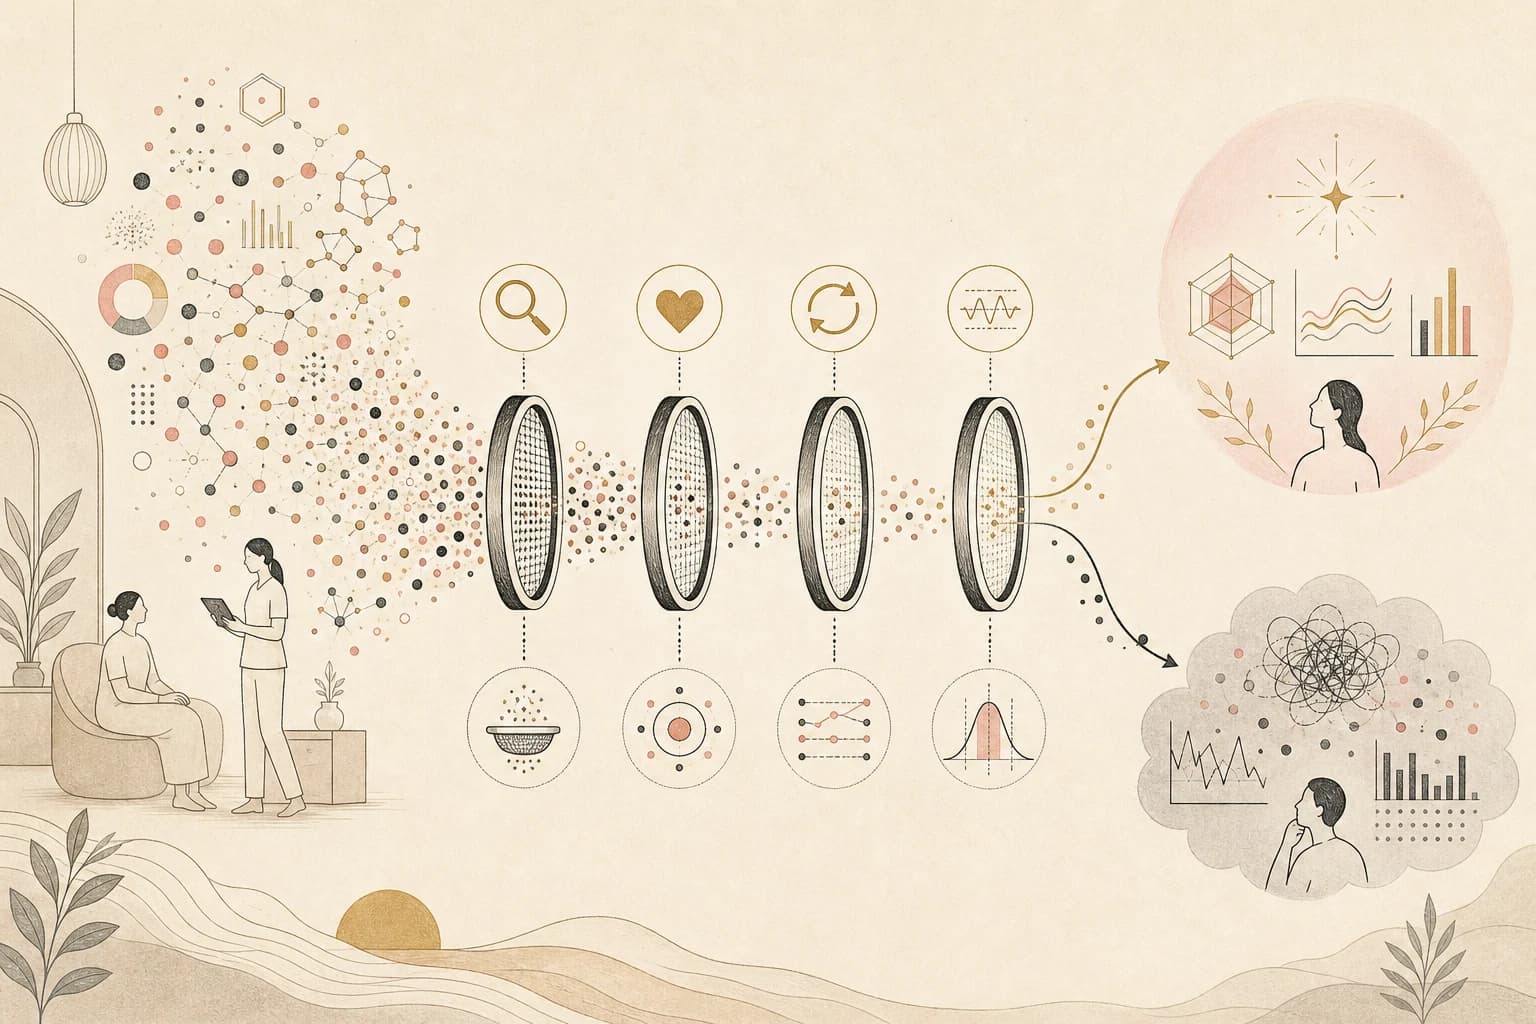
That missing job description matters.1 A response marker may show that something changed in biology without proving that a person feels better, functions better, or has a different disease outcome.1 Before admiring a dashboard, ask what each marker is meant to do and what action follows an unusual result.3 A bundle becomes useful through purpose and follow-up, not through the number of colored tiles.3
NAD+ is named here only as the neutral catalog reference below.
Screening is a pathway, not a blood draw
WHO describes screening as looking for higher risk in people who appear healthy so an early intervention can be offered.6 That definition includes an action after the test.6 A result with no agreed meaning, confirmation plan, or next step is data collection rather than a complete screening pathway.3
Good screening also needs quality assurance and a clear balance of benefits and harms.3 Possible harms include a false alarm, false reassurance, overdiagnosis, and treatment of a finding that would not have caused trouble.3 These are not arguments against screening itself.3 They explain why a screening programme defines the population, test, threshold, follow-up, and informed choice together.3
For a Filipino reader comparing clinic menus, the intended population matters more than the marker count.3
Why normal ranges create red flags
A reference range is built from results in a healthy comparison group.7 It is not a border separating every healthy person from every ill person.7 Someone without disease can land outside the printed interval, while someone with a health problem can still land inside it.7
Many laboratory intervals use the central 95 percent of values.2 Under that convention, 5 percent of healthy people sit outside the interval for one test.2 If 20 independent tests follow the same model, the calculated chance of at least one flag reaches 64.2 percent.2 Real laboratory panels are more complicated because tests may be related and some use decision cutoffs instead.2
The practical lesson is modest: one red box inside a large bundle needs interpretation, not instant alarm.7
The sample has a backstory
Numbers can move for reasons that begin before the needle reaches the arm.8 Food, medicines, supplements, hard exercise, menstruation, and missed preparation instructions can affect some tests.8 The relevant factors differ by test, so a single preparation script does not fit every marker.8
Laboratories may also rely on different methods and reference ranges.8 A result copied from one report should therefore be read against the range printed by that laboratory.8 Method differences can add variation, although they do not explain every change.8
For someone tested after travel, a night shift, training, or a changed supplement routine, this backstory belongs beside the number.8 Context is not an excuse to ignore a result; it is part of deciding what the result means.7
MOTS-c is named here only as the neutral catalog reference below.
More markers do not mean more certainty
The FDA separates three questions about consumer tests.9 Analytical validity asks whether the test measures its target reliably.9 Clinical validity asks whether that measurement relates to the stated health condition.9 The final question is whether the language used to sell or explain the test matches the supporting evidence.9
A crisp report can answer none of these questions by appearance alone.9 The FDA says direct-to-consumer tests carry varying levels of evidence and should not be the sole basis for medical decisions.9 Its US framework does not determine the Philippine status of any clinic or test.9
The useful request is specific: name the method, intended use, comparison range, important limits, and follow-up plan.9 A clinic that can explain those pieces offers more information than a dashboard with extra decimals.9
Two familiar tests show why context wins
Vitamin D and thyroid markers often look ordinary on a wellness menu, yet screening questions remain population-specific.10 In 2021, the USPSTF found insufficient evidence to balance benefits and harms of vitamin D deficiency screening in defined adults without relevant signs, symptoms, or treatment indications.10 That conclusion does not address testing prompted by symptoms or a clinical indication.10
In 2015, the same US task force reached an insufficient-evidence conclusion for thyroid screening in nonpregnant adults without symptoms.11 That statement also has boundaries and does not cover people with symptoms or defined higher-risk conditions.11
Neither example proves that the tests are useless.10 Together, they show why “available in a bundle” and “supported for this asymptomatic person” are different questions.10 A marker earns its place through a reason, not familiarity.3
A flag may start a second question
An unusual result is sometimes the beginning of an inquiry rather than the final label.12 NIDDK explains that clinicians usually use a second blood test to confirm diabetes.12 Different glucose tests measure different aspects of blood sugar, and results can vary.12 The exact response depends on symptoms, the test, and the clinical situation.12
This pattern gives a practical way to judge a wellness bundle.3 Before testing, ask what would count as unusual and what confirmation would follow.3 After testing, ask whether the finding fits the person’s history and whether repeating it under suitable conditions would change the interpretation.8
Follow-up should not be improvised from the color of a portal tile.9 A defined path protects against both dismissal and overreaction.3
A moving biomarker is not the whole outcome
NAD+ research offers a clean example of the marker-outcome gap.4 A randomized crossover study enrolled 13 adults with overweight or obesity and compared six weeks of nicotinamide riboside with placebo.4 Markers of NAD+ synthesis rose in skeletal muscle.4
Several other measures did not change in that protocol.4 The study reported no effects on insulin sensitivity, mitochondrial function, selected lipid and cardiac measures, ambulatory blood pressure, inflammatory markers, or energy metabolism.4 The result belongs to that precursor, population, tissue, outcome set, and six-week period.4 It does not describe a catalog item.4
The fair reading keeps both halves together: the biological marker moved, while several broader outcomes did not.4 A wellness report should preserve that distinction whenever it turns a research marker into a personal score.1
Bottom line
A biomarker bundle is useful when every test has a clear job, suitable context, reliable method, and planned response.3 More markers can also create more incidental flags, especially when reference intervals are treated as disease borders.2 Preparation, laboratory method, symptoms, history, and confirmation can change how one number should be read.8
The sensible question is not whether all wellness data are signal or all are noise.3 It is whether each result can support a defined decision without being stretched beyond its evidence.9 A polished dashboard may organize information well, but design cannot supply clinical meaning.9 Purpose, limits, and follow-up do that work.3
This article is educational research context, not medical advice. Catalog links are neutral references and do not imply a treatment or human-use recommendation.
Frequently asked questions
What is a biomarker in plain language?
A biomarker is a measured sign of a normal process, disease process, or biological response.5 The label covers many kinds of measurements and does not assign a use by itself.5 Its value depends on the exact question, method, population, and decision attached to it.1
Does an outside-range result mean I am unwell?
Not by itself.7 Reference ranges describe results in a healthy comparison group, so healthy people can fall outside them.7 People with health problems may also fall inside.7 The test, symptoms, history, preparation, and other findings shape the interpretation.7
Why can a larger panel produce more flags?
Many intervals contain the central 95 percent of healthy results.2 Under a simplified model with 20 independent tests, the calculated chance of at least one outside-range result is 64.2 percent.2 Real panels differ, but the example shows why more testing can create incidental findings.2
Should every unusual result be repeated?
Not automatically; the next step depends on the marker and situation.12 Diabetes testing illustrates why confirmation may matter: NIDDK says clinicians usually use a second blood test to confirm it.12 Symptoms and clinical urgency can change that pathway.12
How should I compare results across clinic visits?
Check the method and printed reference range before comparing numbers.8 Laboratories can differ in both methods and ranges.8 Also record preparation details, medicines, supplements, hard exercise, and other relevant factors.8 Those details can help explain variation without deciding the meaning alone.8
What should I ask before buying a wellness panel?
Ask what each marker is intended to show, who the test is for, how the laboratory measures it, and what follows a flag.9 Also ask about important limits and confirmation.9 Test evidence ranges widely, and one result should not stand alone as a medical decision.9
Can a biomarker improve while broader outcomes do not?
Yes.1 In one randomized crossover study, muscle markers of NAD+ synthesis rose after nicotinamide riboside, while several metabolic, cardiovascular, and inflammatory measures did not change.4 That result is tied to its small population, protocol, outcomes, and six-week period.4
Sources
Footnotes
-
BEST (Biomarkers, EndpointS, and other Tools) Resource. FDA-NIH BEST definition of a response biomarker and its possible pharmacodynamic use. A marker may become a validated surrogate in a specific context, but that status cannot be assumed from movement alone. ↩ ↩2 ↩3 ↩4 ↩5 ↩6
-
Interpretating Normal Values and Reference Ranges for Laboratory Tests. A 2025 clinical laboratory interpretation review explaining the arithmetic of conventional reference intervals. The calculation is an illustration because results in real panels are not always independent and some tests use clinical decision limits rather than central-95-percent intervals. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Screening programmes: a short guide. Increase effectiveness, maximize benefits and minimize harm. WHO programme guidance covering benefits, harms, implementation, and informed choice. The size and type of benefit or harm vary by condition, test, population, and programme. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15 ↩16 ↩17
-
Nicotinamide riboside supplementation alters body composition and skeletal muscle acetylcarnitine concentrations in healthy obese humans. Randomized, double-blind, placebo-controlled crossover study with broad metabolic phenotyping. The finding is limited to this small study population, precursor, protocol, tissues, outcomes, and six-week period; it is not evidence about a catalog product. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11
-
BEST (Biomarkers, EndpointS, and other Tools) Resource. A terminology resource jointly developed by FDA and NIH to standardize biomarker and endpoint language. The definition does not say that every measurable characteristic is useful for screening or individual care. ↩ ↩2 ↩3 ↩4 ↩5
-
Screening programmes: a short guide. Increase effectiveness, maximize benefits and minimize harm. WHO guidance for planning and evaluating organized screening programmes. This public-health definition does not make every individual wellness test an organized screening programme. ↩ ↩2
-
Interpretating Normal Values and Reference Ranges for Laboratory Tests. A clinical laboratory review of reference intervals, healthy comparison groups, and interpretation. Interpretation depends on the test, symptoms, history, and other clinical information. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9
-
Preanalytical Variables and Their Influence on the Quality of Laboratory Results; Interpretating Normal Values and Reference Ranges for Laboratory Tests. Reviews of preanalytical variables and laboratory-method differences. Not every listed factor affects every test, so preparation and interpretation must be test-specific. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13
-
Direct-to-Consumer Tests. FDA consumer and regulatory overview of direct-to-consumer in-vitro tests. US FDA oversight does not establish Philippine regulatory status for a test or clinic. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7 ↩8 ↩9 ↩10 ↩11 ↩12 ↩13 ↩14 ↩15
-
Screening for Vitamin D Deficiency in Adults: US Preventive Services Task Force Recommendation Statement. US preventive-screening recommendation for a defined asymptomatic adult population. This statement is not a recommendation against diagnostic testing for symptoms or testing people with specific clinical indications. ↩ ↩2 ↩3 ↩4 ↩5
-
Screening for thyroid dysfunction: U.S. Preventive Services Task Force recommendation statement. US preventive-screening recommendation for nonpregnant, asymptomatic adults. The recommendation does not apply to people with signs, symptoms, or specific higher-risk conditions. ↩ ↩2
-
Diabetes Tests and Diagnosis. US NIH patient guidance on diabetes testing and diagnosis. Confirmation and urgency depend on symptoms, the test used, and the clinical situation. ↩ ↩2 ↩3 ↩4 ↩5 ↩6 ↩7